



Dr. Samhitha Reddy
Consultant Proctologist & Laparoscopic Surgeon
MBBS, MS, FMAS, FISCP, DMAS
- 8 Yrs
- ASCRS Member
Do you struggle to button clothes, drop objects often, or feel unsteady when walking? These symptoms may indicate cervical myelopathy, a condition caused by compression of the spinal cord in the neck. Unlike ordinary neck pain or a pinched nerve, cervical myelopathy can affect coordination, balance and strength in both the arms and legs, and because symptoms may develop gradually, early changes are easy to overlook.
At Lux Hospitals, Hyderabad, patients can enquire about spine consultations for suspected cervical spinal cord compression, hand weakness, walking difficulties and other neurological symptoms. Timely assessment is important because progressive spinal cord dysfunction can lead to lasting neurological impairment.
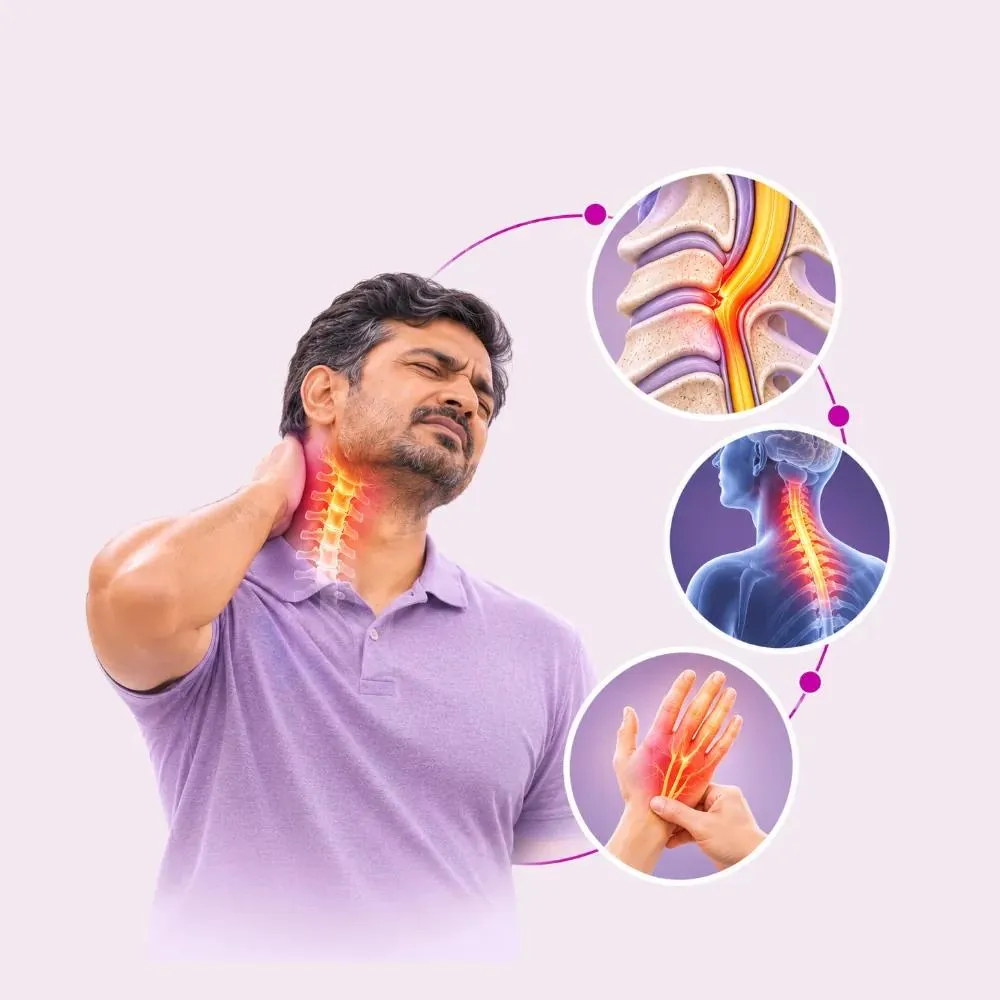
Cervical myelopathy is a condition in which the spinal cord in the neck becomes compressed, affecting the nerve signals responsible for movement, sensation and coordination.
The cervical spine consists of seven vertebrae (C1–C7) that protect the spinal cord. Age-related changes, herniated discs, bone spurs or thickened ligaments can narrow the spinal canal and put pressure on the spinal cord.
Degenerative cervical myelopathy (DCM), sometimes called cervical spondylotic myelopathy, is a common form caused by age-related changes in the cervical spine. Symptoms may include hand clumsiness, balance difficulties, leg stiffness and changes in walking.
Unlike cervical radiculopathy, which involves compression of a nerve root and typically causes pain, tingling or weakness in the arm, cervical myelopathy affects the spinal cord itself. Both conditions can occur together but require different treatment considerations.
Several conditions can narrow the cervical spinal canal and place pressure on the spinal cord.
Cervical spondylosis involves degenerative changes affecting the neck’s discs, joints and bones. These changes can gradually reduce the space available for the spinal cord.
A herniated cervical disc may protrude backwards into the spinal canal and compress the spinal cord.
Degenerative changes can produce bony growths called osteophytes, which may contribute to spinal canal narrowing.
Ossification of the posterior longitudinal ligament (OPLL) occurs when a ligament along the spine becomes abnormally hardened or bone-like. It can narrow the spinal canal and contribute to spinal cord compression.
Age-related thickening or folding of ligaments may reduce the space around the spinal cord.
Some people naturally have a narrower cervical spinal canal, which may increase susceptibility to compression.
Trauma can occasionally contribute to spinal cord compression or worsen an existing narrowed canal.
The underlying cause and degree of neurological impairment help determine treatment.
Symptoms often develop gradually and may initially be mistaken for ageing, arthritis or general weakness.
Common symptoms
Emergency warning signs
Some patients primarily notice changes in their hands or walking ability. Early cervical myelopathy may cause subtle changes such as slower hand movements, reduced finger coordination or occasional loss of balance, and these should not automatically be attributed to normal ageing. The emergency signs need immediate emergency care: spinal cord dysfunction can sometimes become permanent if significant compression continues.
Diagnosis requires careful neurological assessment and imaging of the cervical spine.
The doctor asks about hand coordination, walking difficulties, balance changes, numbness, weakness and how symptoms have progressed. Previous injuries, medical conditions and treatments may also be reviewed.
The clinician evaluates muscle strength, sensation, reflexes, coordination and walking ability. Signs such as increased reflexes, abnormal hand reflexes or muscle stiffness may suggest spinal cord involvement.
The patient may be asked to perform balance or controlled walking tests. These help determine how spinal cord compression affects function.
X-rays may show degenerative changes, spinal alignment abnormalities or other bony findings. They cannot directly show spinal cord compression.
MRI is an important investigation for suspected cervical myelopathy. It provides detailed images of the spinal cord, discs, ligaments and surrounding structures, and may show compression, narrowing or signal changes within the spinal cord.
CT may be useful when detailed assessment of bone structures or OPLL is required. Other investigations may be considered to exclude alternative neurological conditions.
Together, the examination and imaging findings help the doctor judge how severe the myelopathy is and plan treatment.
Treatment depends on neurological severity, the cause of compression and the patient’s overall health. Unlike uncomplicated neck pain, established cervical myelopathy requires careful monitoring because spinal cord function may deteriorate. Non-surgical care may be considered for carefully selected patients with mild, stable degenerative cervical myelopathy, but these measures do not physically remove spinal cord compression.
Appropriate rehabilitation may help maintain mobility, strength and physical function. Exercises should be designed by a qualified professional familiar with cervical spinal cord compression, and forceful neck manipulation or high-velocity cervical adjustments should be avoided in patients with known significant cord compression.
Patients may be advised to avoid high-impact activities, contact sports and situations with a substantial risk of falls or neck injury.
Selected medicines may help relieve associated neck or nerve-related pain. However, medication does not decompress the spinal cord or reliably prevent neurological deterioration.
Patients managed without surgery need follow-up neurological examinations. Any deterioration in hand function, walking, strength or balance should prompt reassessment.
Removes one or more affected cervical discs through an approach from the front of the neck. The spinal cord is decompressed, and the operated vertebrae are stabilised using fusion.
Removes part or all of a vertebral body along with compressive structures when more extensive anterior decompression is required. Spinal reconstruction and stabilisation are then performed.
Removes part of the bony arch at the back of the spine to create additional space for the spinal cord. Fusion may be performed when stability or alignment requires it.
Enlarges the spinal canal by repositioning the bony arch rather than removing it completely. It may be suitable for selected patients with multilevel compression and appropriate spinal alignment.
The surgeon may recommend alternative or combined approaches depending on the number of affected levels, spinal alignment, OPLL and other anatomical factors.
Clinical guidelines recommend surgery for moderate and severe degenerative cervical myelopathy, and it may also be needed in mild cases, especially if symptoms worsen or remain functionally significant. The main goals are to relieve pressure on the spinal cord and prevent further deterioration. Although neurological improvement may occur, full recovery is not guaranteed, and no single procedure is best for every patient.
The surgical approach depends on the location and extent of spinal cord compression. Anterior cervical decompression and fusion is one established technique for selected patients.
Anterior Cervical Decompression and Fusion
The operation is generally performed under general anaesthesia. The anaesthesia team monitors the patient’s vital functions throughout the procedure.
The patient is carefully positioned to provide access to the affected cervical spinal levels. Special precautions may be necessary to avoid worsening existing spinal cord compression.
For an anterior approach, an incision is made at the front of the neck, and the surgeon carefully accesses the affected spinal level.
The damaged disc and any additional compressive tissue are removed as necessary, with the aim of providing adequate space for the spinal cord.
The surgeon assesses the decompressed area and confirms that the planned structures have been addressed.
When fusion is required, an appropriate implant or spacer may be placed to support the operated spinal levels.
The team closes the incision and monitors the patient after anaesthesia, assessing neurological function, swallowing, pain and other relevant postoperative factors.
The approach chosen for you depends on the number of affected levels, your spinal alignment and the cause of compression.
Cervical myelopathy requires careful assessment because spinal cord compression can affect movement, coordination and long-term independence.
Treatment planning considers neurological findings, symptom progression and relevant imaging.
The type and extent of spinal cord compression influence whether surgery is indicated and which approach may be suitable.
Mild, stable symptoms call for different management decisions from progressive or severe myelopathy.
Patients may need neurological monitoring, functional rehabilitation and postoperative care.
Lux Hospitals is located in HITEC CITY, near IKEA, with access from Gachibowli and surrounding areas of Hyderabad.
Recovery after cervical myelopathy treatment depends on the severity of spinal cord dysfunction, how long symptoms have been present and the treatment selected.
Following surgery, patients are monitored for neurological changes, swallowing difficulties, wound concerns and other complications. Walking and suitable movement may begin when medically appropriate.
Pain and incision discomfort may gradually improve. Patients should follow the surgeon’s instructions on neck movement, wound care and daily activities.
Light activities may gradually increase as recovery progresses. Patients who have had fusion may have specific restrictions.
The clinician may recommend rehabilitation focusing on balance, strength and functional movement. Follow-up examinations help monitor neurological recovery.
Some patients continue to improve in walking, hand function and coordination. However, recovery can be incomplete, especially when spinal cord damage was longstanding.
For some people, neurological recovery may continue beyond six months. The severity and duration of spinal cord dysfunction, together with other clinical factors, determine the extent of rehabilitation.
Routine evaluation is needed to monitor strength, balance, coordination and functional recovery.
Exercises are adapted to spinal stability and neurological findings.
Limit contact sports, forceful manipulation and activities with a high risk of falls, based on your health.
Patients who have had fusion should follow procedure-specific activity and imaging recommendations.
Seek urgent evaluation for progressive weakness, new walking difficulties or changes in bladder or bowel function.
Surgery often prevents further deterioration, but some neurological symptoms may improve slowly or remain partially unresolved.
Seek medical evaluation if you notice any of the following:
The cost of cervical myelopathy treatment depends on disease severity, diagnostic investigations and whether the patient requires clinical monitoring or spinal cord decompression surgery. Surgical costs vary by the number of affected cervical levels, procedure type, implants and hospital requirements.
| Procedure | Estimated Cost |
|---|---|
| ACDF / Cervical Spinal Fusion Removes the damaged disc, relieves spinal cord compression and stabilises the spine. | ₹2,00,000 onward |
| Cervical Laminoplasty Widens the spinal canal to relieve pressure on the spinal cord. | Approx. ₹7,27,940 onward |
| Cervical Decompression / Laminectomy Removes bone or tissue to create more space for the spinal cord. | ₹95,000 onward |
| Cervical Disc Replacement Replaces a damaged disc with an artificial disc to preserve movement in selected patients. | ₹2,80,000 onward |
The degree of spinal cord compression and neurological impairment decides whether monitoring or surgery is recommended.
MRI, CT and other tests needed to assess the spinal cord add to the overall cost.
Surgery involving more than one cervical level may require a more extensive procedure.
Fusion, laminoplasty, laminectomy and disc replacement involve different implants and hospital requirements.
Every figure above is an indicative starting price, not a final quotation. After clinical assessment, the hospital can provide a personalised estimate based on the treatment recommended.

Consultant Endoscopic Spine Surgeon
MBBS, MS (Orthopaedics), Fellowship in Spine Surgery (RGUHS)
7 years experience
Common questions about cervical myelopathy, spinal cord compression, surgery and recovery.
Still have questions? Call us at 079 6908 4422
Still have questions? Message us on WhatsApp at 079 6908 4444
Spine assessment at Lux Hospitals, HITEC CITY: a careful neurological examination, monitoring for mild cases, and decompression surgery when it is needed.
Plot No.116, Lumbini Avenue, HITEC CITY, Near IKEA, Hyderabad – 500032













