



Dr. Samhitha Reddy
Consultant Proctologist & Laparoscopic Surgeon
MBBS, MS, FMAS, FISCP, DMAS
- 8 Yrs
- ASCRS Member
Acute pancreatitis is sudden inflammation of the pancreas, and it is one of the more unpredictable conditions in abdominal medicine. Most attacks are mild and settle within a week; a minority become severe and life-threatening, and the difference is not always apparent on day one.
That unpredictability is why early aggressive supportive care matters so much. Our gastrointestinal team at Lux Hospitals, HITEC CITY manages pancreatitis with intensive fluid resuscitation and close monitoring, treats the underlying cause, and provides surgical and endoscopic care for the complications.
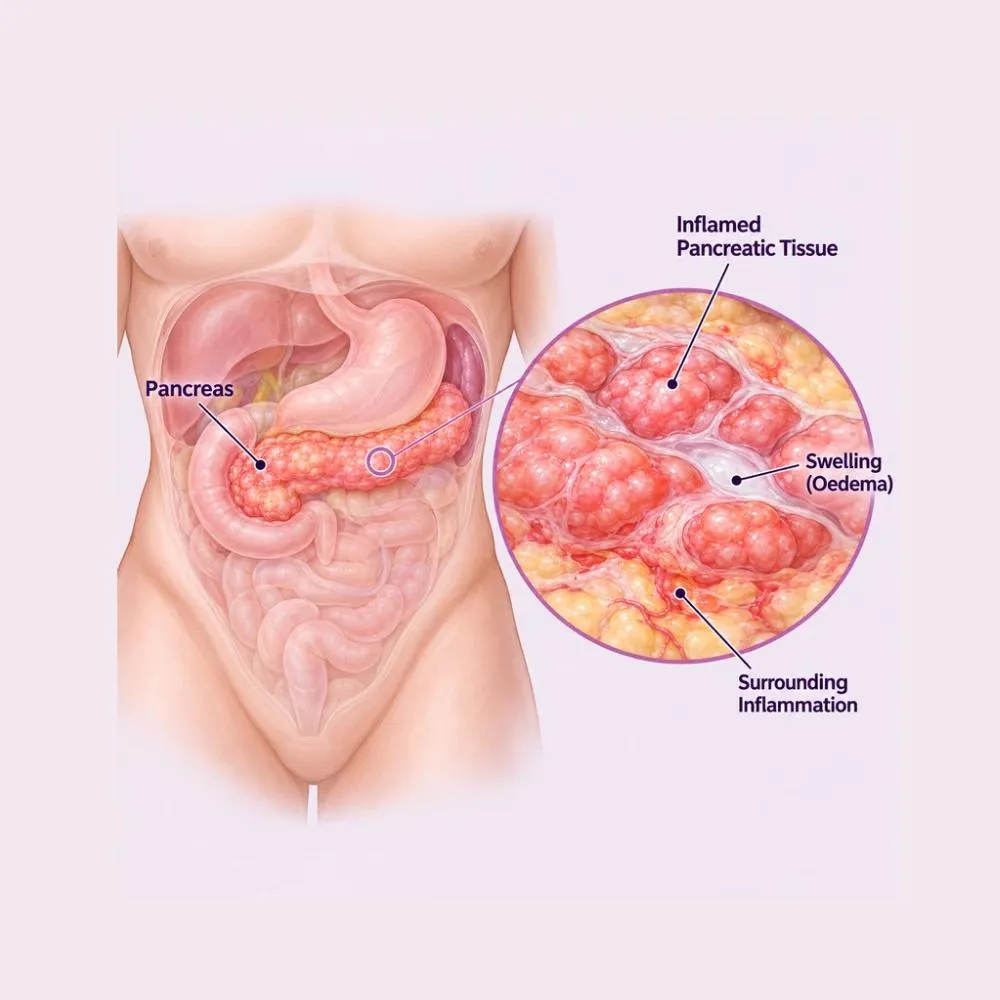
Acute pancreatitis is sudden inflammation of the pancreas, caused when the digestive enzymes it produces become activated inside the gland instead of in the intestine. The pancreas effectively begins digesting itself, and the inflammation that follows can spread well beyond it.
Severity is graded into three. Mild interstitial pancreatitis involves inflammation without tissue death or organ failure, and settles within a week. Moderately severe pancreatitis involves transient organ failure or local complications. Severe necrotising pancreatitis involves persistent organ failure and death of pancreatic tissue, and carries significant mortality.
The illness evolves in phases. The early inflammatory phase gives pain and enzyme rise; the systemic inflammatory phase, over the first week, is when organ failure develops if it is going to; local complications such as fluid collections and necrosis appear from the second week; and then either recovery or progression follows. Knowing which phase someone is in guides what to do, and what not to do yet.
Two causes (gallstones and alcohol) account for around eighty per cent of cases. Identifying which is essential, because gallstone pancreatitis needs the gallbladder removed to prevent recurrence.
The commonest cause. A stone passing through and obstructing the pancreatic duct outlet triggers the enzyme activation that starts the attack.
The second commonest, usually after sustained heavy intake rather than a single episode. Repeated attacks progress toward chronic pancreatitis.
Very raised triglyceride levels directly cause pancreatitis, and this cause is easily missed unless it is specifically tested for.
Certain diuretics, immunosuppressants, some antibiotics and antiretrovirals are recognised triggers.
A recognised complication of endoscopic procedures on the bile and pancreatic ducts, occurring in a small percentage of cases.
A blunt injury to the upper abdomen can damage the pancreas and trigger inflammation.
Raised blood calcium, often from an overactive parathyroid gland, is an uncommon but treatable cause.
In a proportion of cases no cause is found. These warrant careful investigation, since a small pancreatic tumour can present this way.
Finding the cause is not academic. A gallstone attack without gallbladder removal has a high chance of recurrence, sometimes more severely, so the cholecystectomy is part of treating the pancreatitis.
The pain is distinctive: severe, constant, in the upper abdomen, boring through to the back, and often eased slightly by leaning forward.
Typical symptoms
Signs of severe disease
Severe upper abdominal pain going through to the back with vomiting needs emergency assessment, not a wait-and-see approach. The first twenty-four to forty-eight hours of fluid management materially affect the outcome.
The diagnosis needs two of three: characteristic pain, raised enzymes, or imaging findings. Assessing severity matters as much as making the diagnosis.
Raised to three times the upper limit confirms the diagnosis. Lipase is more specific and stays elevated longer, so it is more useful if presentation is delayed.
Performed early to look for gallstones and bile duct dilatation: the crucial question of whether this is gallstone pancreatitis.
Best performed after seventy-two hours, when necrosis becomes visible. Done too early it underestimates the extent of tissue death.
Full blood count, urea, calcium, glucose, LDH and CRP feed into scoring systems that predict severity and guide the level of care needed.
Checked in every case, since both are treatable causes that are easily missed if not specifically looked for.
Used where the cause is unclear, to detect small stones, duct abnormalities or an underlying tumour.
Timing the CT matters. Scanning on day one shows an inflamed pancreas but cannot show necrosis, which takes seventy-two hours to declare itself, so an early normal-looking scan is not reassurance.
There is no drug that treats pancreatitis directly. Treatment is aggressive supportive care while the inflammation runs its course, plus treating the cause and any complications.
Intravenous fluids in the first twenty-four to forty-eight hours, guided by urine output and blood tests. This is the single most important intervention in the early phase.
Strong analgesia, often opioid, given adequately. Under-treating pancreatitis pain is common and serves no purpose.
Feeding by mouth or nasogastric tube as soon as tolerated, usually within twenty-four to forty-eight hours. Prolonged starvation is no longer advised and worsens outcomes.
Intensive care with respiratory, renal and cardiovascular support where organ failure develops.
Insulin and lipid-lowering therapy for triglyceride-induced pancreatitis, stopping a causative drug, or correcting high calcium.
Not given routinely, they do not prevent infection of necrosis, but used where infection is confirmed or strongly suspected.
For gallstone pancreatitis with cholangitis or persistent bile duct obstruction, clearing the stone endoscopically within twenty-four to forty-eight hours.
Gallbladder removal, ideally during the same admission for mild gallstone pancreatitis. Delaying it risks a further, sometimes worse, attack.
Image-guided drainage of infected collections, and often the first step in the step-up approach to necrosis.
Removal of dead pancreatic tissue through an endoscope passed via the stomach wall. Now preferred to open surgery, with markedly lower complication rates.
Video-assisted retroperitoneal debridement, used where the endoscopic route is not feasible.
Now a last resort, reserved for cases where less invasive approaches have failed. It carries substantially higher risk.
The principle in necrotising pancreatitis is to delay and to step up. Intervening early and aggressively worsens outcomes; waiting for necrosis to wall off, then starting with the least invasive option, does better.
Severe pancreatitis is managed over weeks rather than in a single procedure. This is the sequence that has been shown to give the best outcomes.
The step-up approach
Diagnosis confirmed, severity scored, and aggressive intravenous fluids started immediately. The first forty-eight hours matter disproportionately.
Ultrasound for gallstones, triglycerides and calcium checked, and a medication review. Urgent ERCP if there is obstruction with cholangitis.
Enteral feeding started early, by mouth or nasogastric tube. It maintains the gut barrier and reduces the risk of infected necrosis.
Daily assessment for organ failure, with CT after seventy-two hours to define the extent of necrosis and any collections.
Intervention is deliberately delayed for four weeks or more, allowing the necrosis to become walled off. Early debridement substantially increases mortality.
A drain placed under image guidance into the collection. In a meaningful proportion of patients this alone is sufficient, and nothing further is needed.
Where drainage is not enough, dead tissue is removed endoscopically through the stomach wall, often over several sessions.
The instinct to operate early on a very sick patient is understandable and wrong here. Delaying intervention until the necrosis has walled off, and starting with the least invasive step, is what the evidence supports.
Pancreatitis outcomes depend on early resuscitation and on knowing when not to intervene. Here is why patients trust us:
Immediate assessment, aggressive resuscitation and intensive care support, with urgent ERCP available where obstruction demands it.
Led by Dr. Tagore Mohan Grandhi, with extensive experience in pancreatic disease and the step-up management of necrosis.
From the first consultation through to post-treatment follow-up, with one team throughout.
Our hospital is in HITEC CITY, near IKEA: easily reachable from across Hyderabad.
Mild pancreatitis resolves within a week with no lasting damage. Severe disease takes months, and can leave permanent effects on pancreatic function.
Intensive fluid resuscitation and pain control. Severity becomes clearer over this period, and early feeding begins as tolerated.
In mild disease, pain settles, enzymes fall and diet is reintroduced. Cholecystectomy is planned before discharge if gallstones were the cause.
In severe disease, this is the systemic inflammatory phase with the risk of organ failure. CT defines necrosis and collections.
Necrosis walls off and intervention proceeds if needed. Nutritional rehabilitation is central: most patients have lost substantial weight.
Gradual recovery of strength. Assessment for diabetes and exocrine insufficiency, both of which can follow severe pancreatitis.
Absolutely essential if alcohol caused the attack, and advisable regardless. Continued drinking leads to further attacks and chronic pancreatitis.
If gallstones were the cause, cholecystectomy prevents recurrence. Deferring it risks a further and possibly worse attack.
High-protein, low-fat diet in small frequent meals, with dietitian support. Most patients have lost significant weight and muscle.
Where raised lipids caused the attack, lifelong dietary control and medication are needed to prevent it happening again.
Diabetes and enzyme insufficiency (causing fatty, foul-smelling stools) can develop months later and are both treatable.
Review with repeat imaging where collections were present, and testing for diabetes and exocrine function after severe attacks.
Mild pancreatitis usually leaves no lasting damage. After severe necrotising disease, however, a significant proportion of patients develop diabetes or enzyme insufficiency, which is why the follow-up matters even once you feel well.
Any of the following needs immediate assessment.
Cost varies enormously with severity. A mild attack is a few days in hospital; severe necrotising pancreatitis can mean weeks in intensive care.
| Procedure | Estimated Cost |
|---|---|
| Consultation & assessment Per visit | ₹1,000 – ₹2,000 |
| Diagnostic workup Bloods, enzymes, ultrasound and CT | ₹15,000 – ₹35,000 |
| Mild pancreatitis: ward admission Four to seven nights with IV fluids | ₹80,000 – ₹1,80,000 |
| ERCP for gallstone pancreatitis Urgent procedure where indicated | ₹45,000 – ₹85,000 |
| Laparoscopic cholecystectomy Same admission for mild gallstone pancreatitis | ₹65,000 – ₹1,10,000 |
| Severe pancreatitis with ICU care Two to six weeks, organ support | ₹4,00,000 – ₹12,00,000 |
| Endoscopic necrosectomy Often several sessions | ₹2,00,000 – ₹4,50,000 |
By far the largest factor. Mild pancreatitis is a few days on a ward; severe necrotising disease can mean weeks of intensive care.
Ventilation, dialysis and inotropic support in intensive care dominate the cost of severe cases.
Necrosectomy frequently requires several sessions, and each is costed separately.
A shared ward, a twin-sharing room or a private suite: the largest single swing in most estimates.
We are empanelled with most major insurers, and our team files the pre-authorisation for you.
Every figure above is an indicative range, not a quote. After your consultation you are given a written, fixed-cost estimate, and that is the number you pay, with no additions once treatment begins.
The gastrointestinal and pancreatic surgeon who treats acute pancreatitis at our HITEC CITY hospital.

Senior Consultant: Bariatric & Gastrointestinal Surgery
MBBS, MS, FRCS (UK), DLS (France)
28 years experience
Reviews from patients treated for pancreatic and gastrointestinal conditions at Lux Hospitals, Hyderabad.
Written by Dr. Tagore Mohan Grandhi on pancreatic and digestive health.

Dr. Tagore Mohan Grandhi

Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Common questions about acute pancreatitis, its treatment, and what care costs at Lux Hospitals.
Still have questions? Call us at 079 6908 4422
Still have questions? Message us on WhatsApp at 079 6908 4444
Emergency assessment and intensive supportive care for pancreatitis, with the underlying cause identified and treated.
Plot No.116, Lumbini Avenue, HITEC CITY, Near IKEA, Hyderabad – 500032













