



Dr. Samhitha Reddy
Consultant Proctologist & Laparoscopic Surgeon
MBBS, MS, FMAS, FISCP, DMAS
- 8 Yrs
- ASCRS Member
Rectal cancer is treated differently from colon cancer, and the difference is anatomy. The rectum sits low in the bony pelvis with little room around it, which makes clear surgical margins harder to achieve and makes treatment before surgery far more important.
Two questions dominate: can the cancer be cured, and can the sphincter be preserved. Our gastrointestinal surgeon at Lux Hospitals, HITEC CITY stages with pelvic MRI, uses neoadjuvant therapy to shrink the tumour where indicated, and performs total mesorectal excision with sphincter preservation wherever it is oncologically safe.
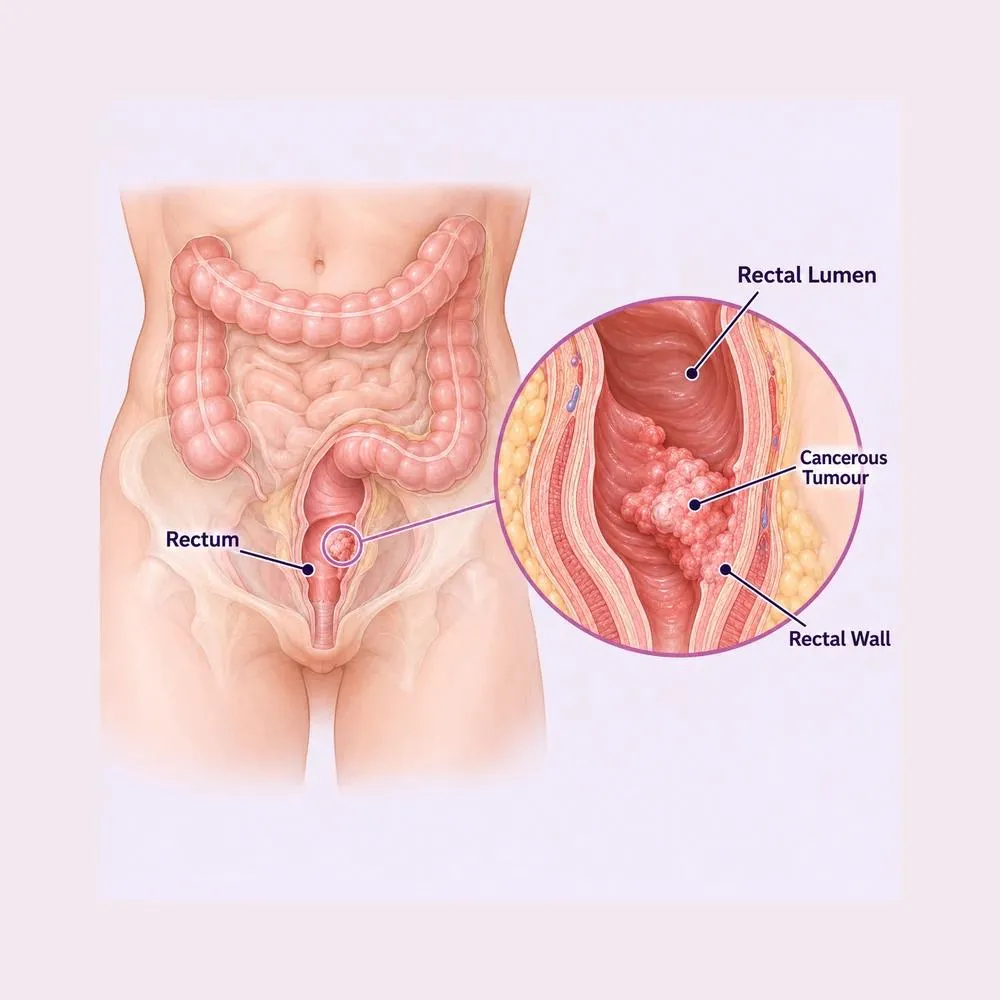
Rectal cancer is a malignant growth arising in the last fifteen centimetres of the large bowel, before the anus. Like colon cancer it usually develops from an adenomatous polyp over years, but its treatment differs substantially because of where it sits.
The rectum is surrounded by a fatty envelope called the mesorectum, which contains its lymph nodes and drainage. Removing that envelope intact (total mesorectal excision) is the single technical factor most strongly associated with avoiding local recurrence. It is why rectal cancer surgery is regarded as a specialist operation rather than a general one.
Staging follows the same scheme as colon cancer, from stage I confined to the rectal lining through to stage IV with distant spread. What differs is the sequence of treatment: rectal cancer beyond the earliest stage is usually treated with radiotherapy and chemotherapy first, and surgery afterwards.
The risk factors are the same as for colon cancer, since the two arise through the same process from the same kind of precursor lesion.
Risk rises steadily after forty-five, which is when routine screening begins for people at average risk.
The direct precursor. Most rectal cancers arise from a polyp over ten to fifteen years, which is why polyp removal prevents them.
A first-degree relative with colorectal cancer roughly doubles the risk and lowers the age at which screening should start.
Lynch syndrome and familial adenomatous polyposis carry very high lifetime risk and need dedicated surveillance.
Long-standing ulcerative colitis involving the rectum raises risk substantially over decades.
High red and processed meat intake with low fibre is consistently associated with increased colorectal cancer risk.
Both independently increase risk, and regular activity is among the more reliably protective factors.
Both raise risk in a dose-related way, and both can be changed at any point.
Rectal cancer is being diagnosed increasingly in people under fifty, for reasons that are not fully explained. Bowel symptoms in a young adult should not be dismissed on the basis of age alone.
Rectal cancer symptoms overlap almost exactly with those of piles, which is the central reason it gets diagnosed late.
Common symptoms
Systemic and advanced symptoms
Rectal bleeding attributed to piles without an examination is the most common route to a late diagnosis. Piles are far more likely, but that is a conclusion to reach after looking, not before.
Colonoscopy with biopsy confirms the diagnosis, but pelvic MRI is what drives the treatment decision: it shows whether the cancer can be cleanly removed.
A gloved finger examination that detects many rectal tumours directly and assesses how far up they sit and whether they are mobile.
Confirms the diagnosis histologically, measures the exact distance from the anal verge, and examines the rest of the colon.
The critical test. It shows tumour depth, involved lymph nodes, and whether the circumferential margin is threatened, which determines whether treatment is needed before surgery.
Staging imaging looking for spread to the liver and lungs, which changes the treatment plan entirely if present.
Full blood count, liver and kidney function, and the CEA tumour marker as a baseline for tracking response and surveillance.
Highly accurate for early tumours, helping identify those suitable for local excision rather than a major resection.
The MRI answers the question that matters most: is the circumferential resection margin threatened? If it is, radiotherapy and chemotherapy come first: going straight to surgery would risk leaving cancer behind.
Rectal cancer treatment is sequenced. Unlike colon cancer, surgery is often not the first step: shrinking the tumour beforehand improves both clearance and the chance of preserving the sphincter.
Five to six weeks of radiotherapy with chemotherapy, followed by surgery eight to twelve weeks later. It shrinks the tumour and reduces local recurrence substantially.
Five days of radiotherapy followed by surgery. Effective and more convenient, though less shrinkage is achieved.
All chemotherapy and radiotherapy given before surgery. It improves completion rates and increases the chance of a complete response.
Where the tumour disappears completely after chemoradiotherapy, close surveillance without surgery is an option in carefully selected patients at specialist centres.
Removal of the rectum with its mesorectal envelope intact, rejoining the colon to the remaining rectum or anal canal. The sphincter-preserving operation.
Removal of the rectum and anus with a permanent colostomy. Necessary where the tumour involves the sphincter itself and cannot be cleared otherwise.
Removal of a small early tumour through the anus, avoiding a major resection entirely in carefully selected stage I disease.
Keyhole approaches to the same operation. Robotic instrumentation is particularly suited to the narrow male pelvis.
A temporary stoma protecting a low join while it heals, typically reversed after three to six months.
Sphincter preservation is achievable in most patients today, largely because neoadjuvant treatment shrinks tumours that would once have required a permanent colostomy. Where the sphincter is directly involved, however, clearing the cancer takes priority.
A three to four hour operation removing the rectum within its intact mesorectal envelope, with a six to eight night stay.
Low anterior resection with total mesorectal excision
Where chemoradiotherapy was given, surgery follows after an interval of eight to twelve weeks, with repeat MRI to reassess response.
General anaesthetic, positioned to allow access to both abdomen and perineum. Ports are placed for a laparoscopic or robotic approach.
The inferior mesenteric artery is divided at its origin, harvesting the full lymph node basin and mobilising the colon for a tension-free join.
The rectum is dissected in the plane outside the mesorectal envelope, keeping it entirely intact. This plane is what determines local recurrence, and the autonomic nerves are preserved alongside it.
The rectum is divided below the tumour with an adequate distal margin, as low as the anal canal where sphincter preservation is possible.
The colon is joined to the remaining rectum or anal canal, often with a pouch or side-to-end join to improve bowel function afterwards.
A temporary ileostomy is usually formed to protect a low anastomosis while it heals, and reversed after three to six months.
The quality of the mesorectal specimen is assessed and graded by the pathologist. An intact mesorectum is the strongest predictor of avoiding local recurrence, which is why the plane of dissection matters so much.
Rectal cancer surgery is technically demanding, and outcomes vary with experience more than in almost any other bowel operation. Here is why patients trust us:
Led by Dr. Tagore Mohan Grandhi, with fellowships in robotic surgery (Korea) and 28 years of gastrointestinal surgical experience.
MRI-guided planning and neoadjuvant therapy used to make sphincter-preserving surgery possible wherever it is oncologically safe.
From the first consultation through to post-treatment follow-up, with one team throughout.
Our hospital is in HITEC CITY, near IKEA: easily reachable from across Hyderabad.
The full pathway typically runs six to twelve months from diagnosis through neoadjuvant therapy, surgery and stoma reversal.
Neoadjuvant chemoradiotherapy where indicated, followed by an interval of eight to twelve weeks and a repeat MRI to assess response.
Enhanced recovery protocol with early feeding and mobilisation. Stoma training begins if an ileostomy was formed.
Home and recovering. Final pathology discussed, including the quality of the mesorectal specimen. Desk work from around four weeks.
Adjuvant chemotherapy where indicated, then ileostomy reversal once treatment is complete and the join has healed.
Surveillance with clinical review and CEA every three to six months, annual CT, and colonoscopy at one year then at intervals.
Frequency, urgency and fragmented emptying after a low join are common and expected. This is low anterior resection syndrome, and it improves over one to two years.
Structured pelvic floor work after reversal genuinely helps continence and reduces urgency. Ask for a referral rather than waiting.
Specialist stoma nurse input before and after surgery. Most patients manage a temporary ileostomy well once shown how.
Most recurrences appear within three years, and many are treatable if found early. Surveillance is what finds them.
Fever, worsening abdominal or pelvic pain, high stoma output with dehydration, or discharge from the wound.
Walking from day one, building progressively. Nutrition and activity both support recovery through chemotherapy.
Changed bowel function after a low join is very common and rarely discussed beforehand as fully as it should be. It improves substantially over the first year or two, and there is genuine help available for it.
Book a consultation if any of the following apply.
Rectal cancer treatment is a sequenced pathway. These are the ranges for its main components.
| Procedure | Estimated Cost |
|---|---|
| Consultation & assessment Per visit | ₹1,000 – ₹2,000 |
| Colonoscopy with biopsy Including histopathology | ₹15,000 – ₹30,000 |
| Pelvic MRI & staging CT The staging that drives the treatment plan | ₹30,000 – ₹60,000 |
| Neoadjuvant chemoradiotherapy Full five to six week course | ₹2,00,000 – ₹4,50,000 |
| Laparoscopic low anterior resection Six to eight nights’ stay | ₹3,50,000 – ₹6,00,000 |
| Robotic-assisted TME Six to eight nights’ stay | ₹5,00,000 – ₹8,50,000 |
| Ileostomy reversal Three to five nights, three to six months later | ₹1,20,000 – ₹2,20,000 |
Early tumours may go straight to surgery. Locally advanced ones need a full course of chemoradiotherapy first, which adds substantially.
A sphincter-preserving resection, an abdominoperineal resection with permanent stoma, and a transanal local excision differ greatly in scale.
A defunctioning ileostomy commits you to stoma supplies and a second operation to reverse it.
A shared ward, a twin-sharing room or a private suite: the largest single swing in most estimates.
We are empanelled with most major insurers, and our team files the pre-authorisation for you.
Every figure above is an indicative range, not a quote. After your consultation you are given a written, fixed-cost estimate, and that is the number you pay, with no additions once treatment begins.
The gastrointestinal and colorectal surgeon who treats rectal cancer at our HITEC CITY hospital.

Senior Consultant: Bariatric & Gastrointestinal Surgery
MBBS, MS, FRCS (UK), DLS (France)
28 years experience
Reviews from patients treated for colorectal and gastrointestinal conditions at Lux Hospitals, Hyderabad.
Written by Dr. Tagore Mohan Grandhi on bowel screening, digestive health and colorectal surgery.

Dr. Tagore Mohan Grandhi

Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Common questions about rectal cancer, its treatment, and what care costs at Lux Hospitals.
Still have questions? Call us at 079 6908 4422
Still have questions? Message us on WhatsApp at 079 6908 4444
MRI-based staging and sphincter-preserving surgery planned by a multidisciplinary team, with costs and insurance confirmed upfront.
Plot No.116, Lumbini Avenue, HITEC CITY, Near IKEA, Hyderabad – 500032













