



Dr. Samhitha Reddy
Consultant Proctologist & Laparoscopic Surgeon
MBBS, MS, FMAS, FISCP, DMAS
- 8 Yrs
- ASCRS Member
Faecal incontinence is far more common than the silence around it suggests. Most people wait years before mentioning it, and in that time it quietly shrinks their world: the journeys not taken, the events declined, the constant mapping of where the toilets are.
It is also very treatable. Our specialists at Lux Hospitals, HITEC CITY offer the full range, from diet and biofeedback through to sacral nerve stimulation and sphincter repair, and the majority of patients improve substantially without ever needing surgery.
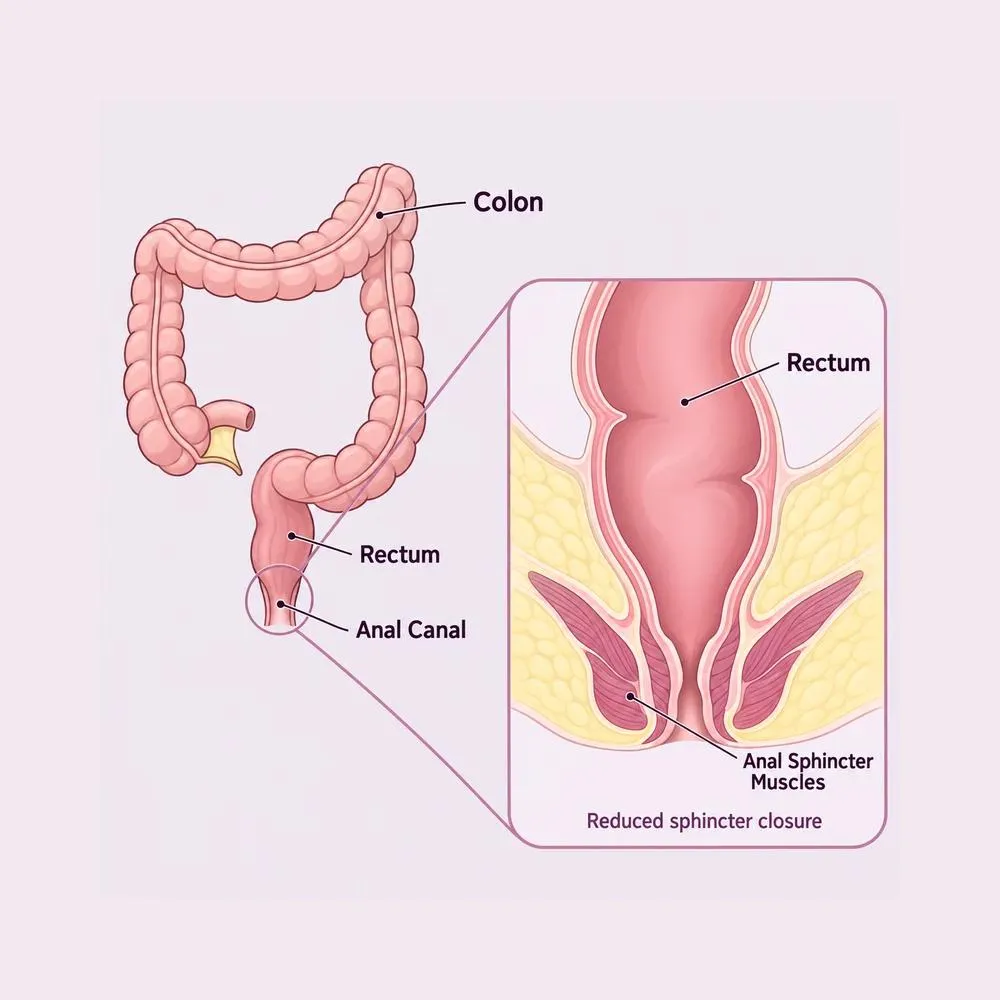
Faecal incontinence is the loss of control over bowel movements, resulting in involuntary leakage of stool. It ranges from occasional leakage of a little stool when passing wind, through to complete loss of bowel control.
Continence depends on several things working together: the two sphincter muscles, the pelvic floor, the sensation that tells you the rectum is filling, and stool that is firm enough to hold. Incontinence follows when any one of them fails, which is why the treatment must be aimed at the specific component that has gone wrong.
There are three patterns. Urge incontinence is a sudden, overwhelming need with leakage before you reach the toilet, and usually reflects a weak external sphincter. Passive incontinence is leakage you are not aware of, pointing to the internal sphincter or to blunted sensation. Overflow incontinence follows chronic constipation, where liquid stool leaks around a hard, impacted mass, and is treated by clearing the constipation, not by strengthening muscles.
Most cases involve damage to the sphincter muscles, the nerves that supply them, or the consistency of the stool itself, and frequently more than one of the three.
The commonest cause in women. Tearing of the anal sphincter during childbirth, sometimes unrecognised at the time, with symptoms appearing years or decades later.
Previous anal surgery (for fistula, fissure or piles) can divide or weaken the sphincter, particularly where a wide sphincterotomy was performed.
Diabetes, multiple sclerosis, spinal injury or a stroke disrupt the signals controlling the sphincter and the sensation of rectal filling.
Loose stool is far harder to hold than formed stool. IBS, IBD and infections all cause incontinence in people whose sphincter is otherwise adequate.
A hard impacted mass in the rectum stretches the sphincter open while liquid stool leaks around it: a common and very treatable cause.
Sphincter strength and pelvic floor tone decline naturally with age, which often unmasks damage sustained decades earlier.
Prolapsing bowel holds the sphincter open and stretches it, and repairing the prolapse usually improves the continence with it.
Large or prolapsed piles prevent the anus closing completely, allowing mucus and stool to seep past.
Identifying which of these applies is the whole of the diagnostic effort, because overflow incontinence and sphincter injury need almost opposite treatments.
Recognising the pattern is what directs treatment, so the details of when and how leakage happens genuinely matter.
Bowel control symptoms
Associated effects
This is not an inevitable part of ageing and it is not something to simply live with. It is a treatable medical condition, and the only genuinely difficult part is the first sentence in the consulting room.
The assessment is thorough but entirely tolerable, and it is done privately. The aim is to establish which component of continence has failed and how severely.
A two-week diary of frequency, urgency, stool consistency and leakage episodes. It is the single most informative part of the assessment.
Inspection for scarring, prolapse, piles or a patulous anus, and assessment of resting tone and voluntary squeeze on rectal examination.
Measures resting and squeeze pressures objectively, and tests rectal sensation. It distinguishes a weak internal from a weak external sphincter.
Images both sphincter rings directly and shows the exact size and position of any tear: the test that decides whether surgical repair is possible.
Where an internal prolapse or rectocele is suspected as the underlying driver of the leakage.
To exclude inflammatory bowel disease, a tumour or another cause where diarrhoea or bleeding accompanies the incontinence.
Bring the bowel diary honestly filled in. Nothing in it will surprise us, and an accurate picture of what actually happens is what makes the treatment work.
Most patients improve substantially without surgery. Treatment is staged, and the great majority never move past the first list.
Firming stool with soluble fibre such as psyllium, and identifying and avoiding the foods that loosen it: caffeine, alcohol, spicy and fatty foods, and artificial sweeteners.
Loperamide to firm stool and increase sphincter tone, fibre supplements to add bulk, or laxatives where overflow from constipation is the cause.
Structured, supervised strengthening of the muscles controlling the bowel. Effective, but only when done correctly, which is why supervision matters.
Sensors and real-time visual feedback teach you to contract the right muscles and restore rectal sensation. The most effective non-surgical treatment available, with good results in around two thirds of patients.
Gentle electrical currents strengthen the anal sphincter, used alongside pelvic floor training where the muscle is weak.
Scheduled toilet visits and, where appropriate, rectal irrigation to empty the bowel predictably so accidents cannot happen between times.
A gel injected into the anal canal wall thickens it and improves closure. A day-care procedure, particularly useful for passive leakage.
A small implanted device modulates the nerves controlling the bowel and sphincter. Highly effective and, importantly, trialled with a temporary wire first so you know whether it works before anything is implanted.
The torn ends of the sphincter are identified and overlapped surgically. The right operation for a discrete tear, most often following obstetric injury.
Where prolapse is the underlying cause, repairing it improves continence in most patients as the sphincter is no longer held open.
An inflatable cuff placed around the anal canal, reserved for severe incontinence where other treatments have failed.
A last resort, but one that some patients with severe refractory incontinence actively choose: it reliably restores predictability and, with it, freedom.
The order matters. Diet, medication and biofeedback are tried first because they help most people, carry no risk, and cost far less than anything on the second list.
The most effective non-surgical treatment for faecal incontinence. A course of outpatient sessions with no anaesthetic, no incision and nothing to recover from.
Anorectal biofeedback & pelvic floor retraining
Anorectal manometry establishes your resting tone, squeeze strength, how long you can hold a squeeze, and how well you sense rectal filling.
A small sensor gives real-time feedback on a screen. Many patients discover they have been squeezing the abdomen or buttocks rather than the sphincter.
Structured exercises to build both maximum squeeze pressure and endurance: the ability to hold, which is what actually buys you time to reach a toilet.
Where sensation is blunted, a small balloon is used to restore awareness of filling at progressively smaller volumes, so you get earlier warning.
Practising the squeeze response to the sensation of urgency until it becomes automatic rather than a conscious effort.
Daily exercises between sessions, with a course typically running six to eight sessions over as many weeks, and a formal review at the end.
Improvement is gradual and depends heavily on the home exercises between sessions. Patients who do them consistently do markedly better than those who rely on the sessions alone.
This condition needs a team that treats it as routine, because for the person raising it, it is anything but. Here is why patients trust us:
Consultations in private, without an audience, and with staff for whom this is an everyday conversation.
Proctologists offering care that addresses both the physical and the psychological weight of the condition.
From the first consultation through to post-treatment follow-up, with one team throughout.
Our hospital is in HITEC CITY, near IKEA: easily reachable from across Hyderabad.
Improvement in continence builds gradually rather than arriving at once. The timeline below is what a typical non-surgical course looks like.
Diet adjusted and medication started. Firming the stool alone produces a noticeable improvement for many patients within days.
Biofeedback sessions run through this period. Squeeze strength and warning time improve steadily with the daily home exercises.
Formal reassessment. Most patients have improved substantially; those who have not are considered for procedural options.
Where surgery or sacral nerve stimulation is chosen, this is when it happens: after conservative treatment has had a genuine trial.
Pelvic floor exercises continue indefinitely, like any other muscle training. Stopping them is the usual reason improvement slips away.
Pelvic floor strength behaves like any other muscle: it fades when training stops. This is a permanent habit, not a course you finish.
Soluble fibre such as psyllium, adequate fluid, and avoiding your trigger foods. Formed stool is far easier to hold than loose.
Emptying at a predictable time each day means there is less in the rectum to leak at unpredictable ones.
Gentle cleansing, thorough drying and a barrier cream. Skin soreness is a common and entirely preventable complication.
It tracks progress objectively and identifies which foods and situations are still causing problems.
The psychological impact is real and it is treatable too. Please raise it: it is a routine part of what we manage here.
The great majority of patients get meaningful improvement, and many get complete control back. The one genuine barrier is how long people wait before asking.
Book a consultation if any of the following apply.
Most patients are treated in the outpatient department. These are the ranges our patients fall into.
| Procedure | Estimated Cost |
|---|---|
| Specialist consultation Per visit, including a management plan | ₹800 – ₹1,500 |
| Anorectal manometry Out-patient, no admission | ₹6,000 – ₹12,000 |
| Endoanal ultrasound Out-patient | ₹5,000 – ₹10,000 |
| Biofeedback therapy course Six to eight out-patient sessions | ₹18,000 – ₹35,000 |
| Injectable bulking agent Day care, same-day discharge | ₹45,000 – ₹80,000 |
| Sphincter repair (sphincteroplasty) Two to three nights’ stay | ₹1,00,000 – ₹1,70,000 |
| Sacral nerve stimulation Includes trial phase and implanted device | ₹4,50,000 – ₹7,50,000 |
Overflow incontinence from constipation may need nothing more than a laxative regimen. A full sphincter tear needs imaging and surgery.
Most patients need six to eight sessions, and some benefit from a top-up course later to consolidate the gains.
Sacral nerve stimulation is dominated by the price of the implanted device, which is why the temporary trial comes first.
A shared ward, a twin-sharing room or a private suite: the largest single swing in most estimates.
We are empanelled with most major insurers, and our team files the pre-authorisation for you.
Every figure above is an indicative range, not a quote. After your consultation you are given a written, fixed-cost estimate, and that is the number you pay, with no additions once treatment begins.
The proctologists and pelvic floor specialists who treat faecal incontinence at our HITEC CITY hospital.

Consultant Proctologist & Laparoscopic Surgeon
MBBS, MS, FMAS, FISCP, DMAS
8 years experience

Consultant General & Advanced Laparoscopic Surgeon
MBBS, MS, FMAS
17 years experience
Reviews from patients treated for pelvic floor and colorectal conditions at Lux Hospitals, Hyderabad.
Written by Dr. Samhitha Reddy on pelvic floor health, bowel control and colorectal conditions.
Dr. Samhitha Reddy


Dr. Samhitha Reddy

Dr. Samhitha Reddy

Dr. Samhitha Reddy

Dr. Samhitha Reddy
Common questions about faecal incontinence, its treatment, and what care costs at Lux Hospitals.
Still have questions? Call us at 079 6908 4422
Still have questions? Message us on WhatsApp at 079 6908 4444
Discreet, expert assessment of bowel control problems, with a clear treatment plan and costs shared upfront.
Plot No.116, Lumbini Avenue, HITEC CITY, Near IKEA, Hyderabad – 500032













