



Dr. Samhitha Reddy
Consultant Proctologist & Laparoscopic Surgeon
MBBS, MS, FMAS, FISCP, DMAS
- 8 Yrs
- ASCRS Member
Abdominal tuberculosis is difficult to diagnose and entirely curable once it is. Its symptoms (abdominal pain, fever, weight loss, altered bowel habit) imitate Crohn’s disease and cancer closely enough that it is frequently mistaken for both.
Getting the diagnosis right matters enormously, because the treatment is a full course of anti-tubercular drugs rather than surgery. Our gastrointestinal team at Lux Hospitals, HITEC CITY establishes the diagnosis properly and reserves surgery for the complications that genuinely need it.
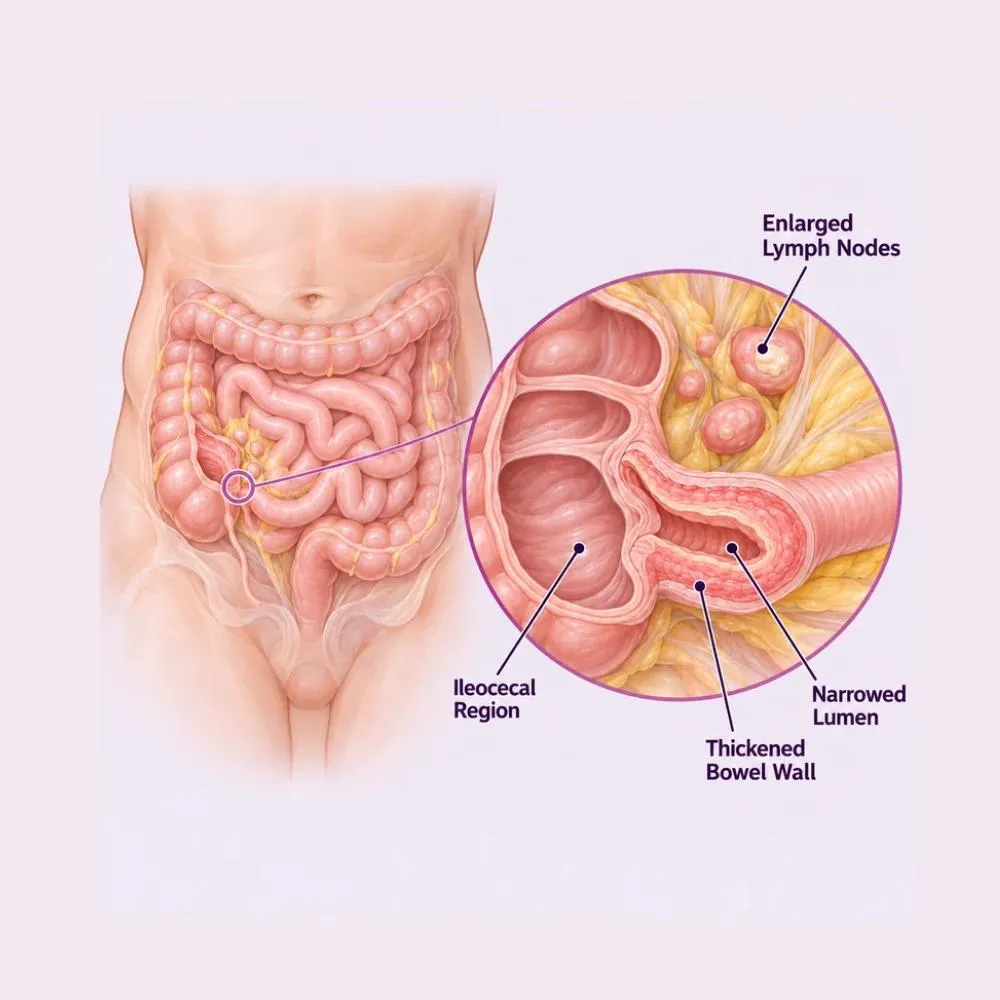
Abdominal tuberculosis is infection of the abdominal organs by Mycobacterium tuberculosis: the same organism that causes lung TB. It remains common in India, and it is among the most frequently missed diagnoses in gastroenterology because it mimics other conditions so closely.
It takes several forms. Intestinal tuberculosis most often affects the ileocaecal region, causing ulcers, thickening and strictures. Peritoneal tuberculosis causes ascites and adhesions between loops of bowel. Lymph node tuberculosis produces enlarged, often matted abdominal nodes. Solid organ involvement of the liver or spleen is less common.
The central diagnostic difficulty is its resemblance to Crohn’s disease. Both cause ileocaecal inflammation, strictures, abdominal pain and weight loss, and they look remarkably similar at colonoscopy. The distinction is critical, because steroids given for presumed Crohn’s disease in a patient who actually has TB will make the infection considerably worse.
The organism reaches the abdomen by several routes, most often from an existing lung infection that may itself be silent.
The commonest route. Bacteria from active pulmonary TB are swallowed and seed the intestinal wall, particularly the ileocaecal region.
Haematogenous spread from a primary lung focus, which may be old, small and entirely asymptomatic.
Extension from infected abdominal lymph nodes, fallopian tubes or other structures into the peritoneum.
Mycobacterium bovis from unpasteurised dairy, now uncommon where pasteurisation is routine.
HIV, diabetes, chronic kidney disease, malnutrition and immunosuppressive therapy all substantially raise the risk.
Biologic drugs used for Crohn’s disease and rheumatoid arthritis can reactivate latent TB, which is why screening before starting them is mandatory.
Household or workplace exposure to someone with untreated pulmonary tuberculosis.
Overcrowding, undernutrition and limited access to healthcare all contribute to the continued prevalence in parts of India.
Around a fifth of patients with abdominal TB have active lung disease as well, which is why a chest X-ray is part of the assessment for everyone.
Symptoms develop insidiously over weeks to months, which is part of why the diagnosis is so often delayed.
Common symptoms
Signs of complications
Evening fever with night sweats, weight loss and abdominal pain over months is the classic picture, and in India it should raise abdominal TB early rather than after everything else has been excluded.
Confirming TB microbiologically can be difficult, and in practice a proportion of patients are treated on strong clinical and radiological grounds rather than on a positive culture.
Shows ileocaecal thickening, necrotic lymph nodes, ascites and peritoneal thickening: a pattern often characteristic enough to strongly suggest TB.
Examines the ileocaecal region directly and takes multiple biopsies. Caseating granulomas on histology are diagnostic, though they are not always found.
GeneXpert PCR on tissue or fluid gives a rapid answer and detects rifampicin resistance. Culture is definitive but takes six to eight weeks.
A high protein, lymphocyte-predominant fluid with raised adenosine deaminase strongly supports peritoneal tuberculosis.
Around a fifth of patients have concurrent pulmonary TB, which is easier to confirm microbiologically and settles the diagnosis.
Where the diagnosis remains uncertain, direct inspection of the peritoneum with targeted biopsy is often what finally confirms it.
Distinguishing TB from Crohn’s disease is the central task, and it is genuinely difficult. Getting it wrong in the direction of Crohn’s, and giving steroids or biologics, disseminates the infection, which is why the effort matters.
Abdominal TB is cured with medication. Surgery treats its complications, and is not the treatment for the infection itself.
Two months of four drugs (isoniazid, rifampicin, pyrazinamide and ethambutol) taken daily. Symptoms usually improve markedly within weeks.
Four to seven further months of isoniazid and rifampicin, giving a total course of six to nine months. Completing it is what prevents relapse and resistance.
High-protein, high-calorie diet with vitamin supplementation. Most patients are significantly malnourished at diagnosis.
Liver function checked regularly, since these drugs can cause hepatitis. Vision is monitored on ethambutol.
Where resistance is detected, second-line regimens are used under specialist supervision for a considerably longer period.
Corticosteroids alongside anti-tubercular therapy where extensive peritoneal adhesions are present, to reduce fibrosis.
Where a stricture does not respond to medication, the narrowed segment is resected or widened by stricturoplasty.
Resection of the perforated segment with washout. An emergency, and the most serious complication of intestinal TB.
Division of dense peritoneal adhesions causing recurrent obstruction, though this is approached cautiously given the risk of injury.
Both diagnostic and, where a limited stricture is found, sometimes therapeutic in the same sitting.
Image-guided drainage of a tubercular abscess, alongside the full course of medication.
The important message is that surgery does not cure abdominal TB and never replaces the drug course. Where an operation is performed for obstruction, the full six to nine months of medication still follows.
A structured course of tablets rather than a procedure. Simple in principle, and it fails almost entirely when the course is not completed.
Six to nine month drug regimen
Imaging, biopsy, PCR and fluid analysis, with a chest X-ray for everyone. Treatment is sometimes started on strong clinical grounds where tissue confirmation is not obtained.
Liver and kidney function, HIV status, blood sugar, weight and vision assessment before drugs are started.
Four drugs daily, dosed by body weight. Fever and night sweats typically settle within two to four weeks, and appetite returns.
Clinical review, weight gain and repeat imaging at two months. A good response supports the diagnosis where it was not microbiologically proven.
Two drugs for a further four to seven months. Most patients feel entirely well by this stage, which is exactly when adherence slips.
Regular liver function tests, and prompt review for jaundice, rash, visual change or numbness in the hands and feet.
Final assessment with repeat imaging to confirm resolution, and follow-up for relapse over the subsequent year.
The single greatest risk to a cure is stopping early. Feeling completely well after two months is expected, and stopping at that point is how treatment failure and drug resistance happen.
The whole challenge here is the diagnosis, and the consequences of getting it wrong are significant. Here is why patients trust us:
Imaging, colonoscopy, PCR and laparoscopy where needed, because distinguishing TB from Crohn’s disease and cancer determines everything that follows.
Led by Dr. Tagore Mohan Grandhi, with extensive experience in abdominal tuberculosis and its surgical complications.
From the first consultation through to post-treatment follow-up, with one team throughout.
Our hospital is in HITEC CITY, near IKEA: easily reachable from across Hyderabad.
Most patients feel markedly better within a month of starting treatment. The full course still runs six to nine months, and completing it is what secures the cure.
Fever and night sweats settle, usually within two to four weeks. Appetite begins returning and weight stabilises.
Intensive phase with four drugs. Weight gain begins. Monthly liver function monitoring throughout.
Response assessed with clinical review, weight and repeat imaging. The regimen steps down to the continuation phase.
Continuation phase. Most patients feel completely well, which is precisely when adherence becomes the main risk.
Final imaging to confirm resolution, with follow-up over the following year to detect any relapse.
Six to nine months without interruption, even after you feel completely well. Stopping early causes relapse and drug resistance.
Adequate protein and calories with vitamin supplementation. Weight gain is one of the clearest signs treatment is working.
Jaundice, severe nausea, rash, visual change or numbness in the hands and feet need reporting promptly: do not simply stop the tablets.
Family members should be assessed, particularly if pulmonary TB is present, since that form is contagious.
Diabetes impairs the response to TB treatment. Tight control materially improves the outcome.
Monthly during treatment for monitoring, then follow-up after completion to confirm cure and detect relapse.
Abdominal tuberculosis is curable in the great majority of patients who complete their treatment. The cure rate is excellent, and it depends almost entirely on finishing the course rather than on anything more complicated.
Book a consultation if any of the following apply.
The medication itself is inexpensive, and available free through government programmes. Most of the cost lies in reaching the diagnosis.
| Procedure | Estimated Cost |
|---|---|
| Consultation & assessment Per visit | ₹1,000 – ₹2,000 |
| CT abdomen with contrast Key diagnostic imaging | ₹6,000 – ₹14,000 |
| Colonoscopy with biopsy Including histopathology and TB PCR | ₹15,000 – ₹30,000 |
| Diagnostic laparoscopy Where the diagnosis remains unclear | ₹60,000 – ₹1,20,000 |
| Anti-tubercular medication Per month; free under government programmes | ₹1,500 – ₹4,000 |
| Monitoring blood tests Per test, monthly during treatment | ₹800 – ₹2,000 |
| Surgery for obstruction or perforation Five to ten nights’ stay | ₹2,00,000 – ₹4,50,000 |
Some patients are diagnosed on CT and colonoscopy. Others need laparoscopy, which is the largest single diagnostic cost.
Uncomplicated abdominal TB is treated entirely with tablets. Obstruction or perforation means major surgery.
Resistant TB requires second-line drugs for a considerably longer period, at substantially greater cost.
A shared ward, a twin-sharing room or a private suite: the largest single swing in most estimates.
We are empanelled with most major insurers, and our team files the pre-authorisation for you.
Every figure above is an indicative range, not a quote. After your consultation you are given a written, fixed-cost estimate, and that is the number you pay, with no additions once treatment begins.
The gastrointestinal surgeon who treats abdominal tuberculosis at our HITEC CITY hospital.

Senior Consultant: Bariatric & Gastrointestinal Surgery
MBBS, MS, FRCS (UK), DLS (France)
28 years experience
Reviews from patients treated for gastrointestinal conditions at Lux Hospitals, Hyderabad.
Written by Dr. Tagore Mohan Grandhi on digestive health and gastrointestinal surgery.

Dr. Tagore Mohan Grandhi

Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Common questions about abdominal tuberculosis, its treatment, and what care costs at Lux Hospitals.
Still have questions? Call us at 079 6908 4422
Still have questions? Message us on WhatsApp at 079 6908 4444
Careful diagnosis and a complete course of treatment for abdominal tuberculosis, with costs shared upfront.
Plot No.116, Lumbini Avenue, HITEC CITY, Near IKEA, Hyderabad – 500032













