



Dr. Samhitha Reddy
Consultant Proctologist & Laparoscopic Surgeon
MBBS, MS, FMAS, FISCP, DMAS
- 8 Yrs
- ASCRS Member
The mini gastric bypass achieves what a traditional bypass achieves, through one join instead of two. That single difference makes the operation shorter, technically simpler and easier to revise if it ever needs to be.
Weight loss and diabetes results are comparable to the Roux-en-Y. Our bariatric team at Lux Hospitals, HITEC CITY performs it laparoscopically, with a two to three night stay and the same lifelong nutritional follow-up any bypass requires.
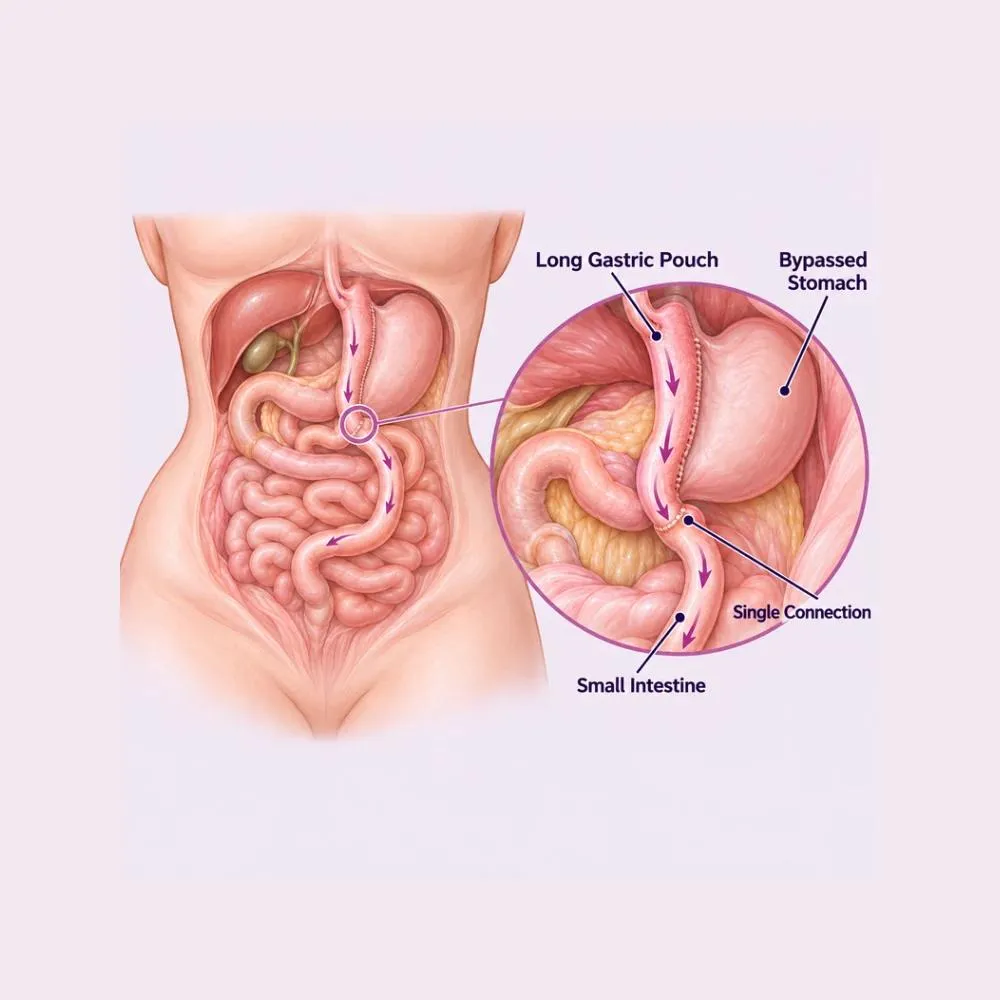
The mini gastric bypass, also called a one-anastomosis gastric bypass, creates a long narrow tube from the upper stomach and joins it directly to a loop of small intestine roughly two metres downstream. Food therefore bypasses the lower stomach, the duodenum and a length of jejunum.
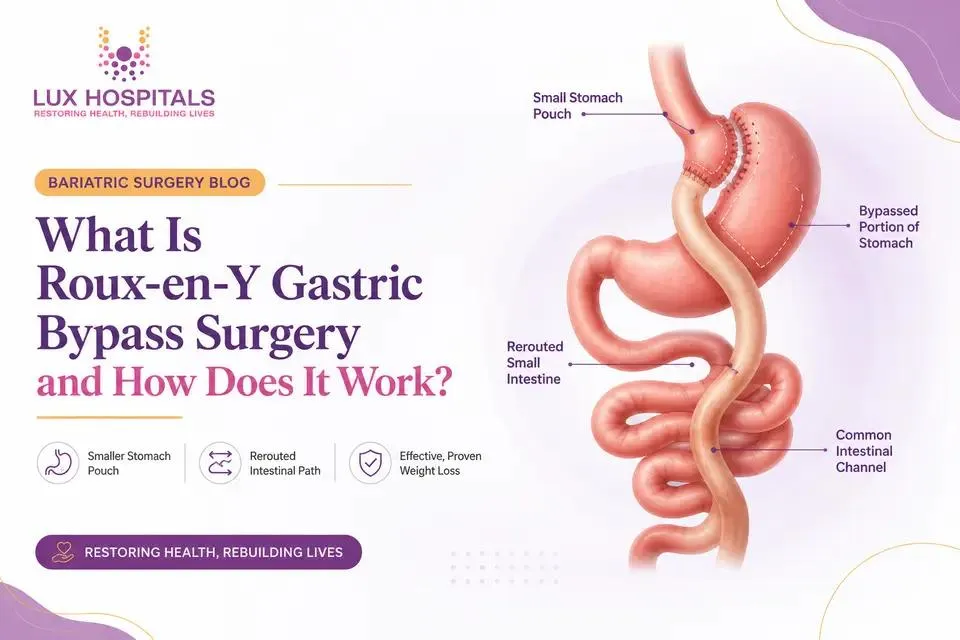
The difference from a Roux-en-Y is the number of connections. A traditional bypass makes two joins and divides the intestine to form a Y; the mini bypass makes a single join to an intact loop. Fewer connections means less operating time, fewer staple lines to leak, and no mesenteric defects to close, which removes the risk of internal hernia entirely.
It is not a smaller operation in effect, only in complexity. The length of intestine bypassed is comparable, so weight loss and the hormonal effect on diabetes are similar. The recognised trade-off is bile reflux: bile can wash up into the stomach pouch in a minority of patients, and where it does, conversion to a Roux-en-Y resolves it.
The mechanisms are the same as any bypass: restriction, reduced absorption and a substantial hormonal effect.
The long narrow gastric tube holds far less than a normal stomach, producing fullness after small portions.
Bypassing around two metres of small intestine means fewer calories are absorbed from what is eaten.
Food reaching the lower intestine rapidly triggers a large hormonal release that boosts insulin and suppresses appetite.
Excluding the duodenum switches off signals promoting insulin resistance, independently of weight loss.
The bypassed portion of stomach produces less hunger hormone, so appetite falls noticeably.
Altered bile circulation improves glucose metabolism and reduces liver fat.
The length of intestine bypassed can be tailored to BMI, giving the surgeon a lever the sleeve does not offer.
Gut bacterial composition changes measurably in patterns associated with improved metabolic health.
Because a longer segment of intestine is bypassed than in a standard Roux-en-Y, nutritional monitoring afterwards matters just as much: arguably more.
The eligibility criteria are the same as for other bariatric surgery. What tends to favour this particular operation is a wish for bypass results with a shorter, simpler procedure.
You may be a candidate if
It is particularly suitable when
It is generally avoided in patients with significant existing acid reflux or Barrett’s oesophagus, where a Roux-en-Y is the safer choice because of the bile reflux risk.
The workup is the same as for any bypass, with particular attention to reflux: since bile reflux is this operation’s main drawback.
Weight history, previous weight-loss attempts, comorbidities and a full medication review.
HbA1c, lipids, liver and kidney function, thyroid, and a full nutritional panel including B12, iron, folate and vitamin D.
Essential. It assesses existing reflux, oesophagitis and Barrett’s oesophagus: any of which makes a Roux-en-Y the better choice.
For gallstones and fatty liver, since rapid weight loss after bypass frequently precipitates gallstones.
ECG, echocardiogram where indicated, and a sleep study for suspected sleep apnoea.
Eating pattern assessment and detailed counselling on the lifelong supplement regime.
Existing reflux is the finding that most often steers a patient away from this operation and toward a Roux-en-Y. That is precisely why the endoscopy comes before the decision.
Surgery follows genuine attempts at non-surgical management. Among the operations, the choice turns on your reflux, your diabetes and your surgical risk.
Dietitian-led planning with regular review, which continues after any operation.
Graded activity with behavioural work on eating patterns and habits.
GLP-1 receptor agonists produce meaningful weight loss through the same hormonal pathway.
A temporary endoscopic device giving six to twelve months of restriction.
A single anastomosis, shorter operating time, no internal hernia risk, and results comparable to a Roux-en-Y. Bile reflux is the recognised trade-off.
Two anastomoses and a longer operation, but no bile reflux: the safer choice where reflux already exists.
Simpler still, with no rerouting and better absorption, but slightly less weight loss and a tendency to worsen reflux.
The standard remedy where troublesome bile reflux develops after a mini bypass, and it resolves it reliably.
A mini bypass is a common and straightforward revision for a sleeve that has produced inadequate weight loss.
For a patient with no reflux who wants bypass-level results from a shorter operation, this is an excellent choice. For someone with existing reflux, the Roux-en-Y is the better one.
A ninety minute to two hour keyhole operation through five small incisions, noticeably shorter than a Roux-en-Y, followed by a two to three night stay.
Laparoscopic one-anastomosis gastric bypass
A two-week liver-shrinking diet to reduce the fatty liver overlying the stomach and make access safer.
General anaesthetic. The abdomen is inflated with carbon dioxide and five ports are placed across the upper abdomen.
A long narrow tube is stapled from the upper stomach down along the lesser curvature: longer than a Roux-en-Y pouch, which reduces bile exposure.
The small intestine is measured from the duodenojejunal flexure, typically to around two metres, with the length tailored to your BMI.
That loop of intestine is joined directly to the end of the gastric tube. This is the only join in the operation: hence the name.
The single join is tested with dye or air under water to confirm it is watertight. With one anastomosis there is one place to check rather than two.
Sips of water the same evening, walking within hours, clear fluids the next day, and home after two to three nights with a detailed diet plan.
Because the intestine is never divided, there are no mesenteric defects and therefore no risk of the internal hernia that can follow a Roux-en-Y years later. That is a genuine long-term advantage.
Choosing between the bypass variants requires a surgeon who performs all of them and has no reason to favour one. Here is why patients trust us:
Led by Dr. Tagore Mohan Grandhi, with fellowships in bariatric surgery (USA) and robotic surgery (Korea) and 28 years of experience.
Sleeve, mini bypass and Roux-en-Y all performed here, so the choice is made on your endoscopy and your diabetes rather than on what we offer.
From the first consultation through to post-treatment follow-up, with one team throughout.
Our hospital is in HITEC CITY, near IKEA: easily reachable from across Hyderabad.
Recovery follows the same pattern as any bypass. The supplement regime is lifelong, and because a longer segment of intestine is bypassed, monitoring matters particularly here.
In hospital. Sips of water the same evening, walking within hours, clear fluids from day one. Home after two to three nights.
Clear liquids and sugar-free, non-carbonated drinks only. Small frequent sips, protein supplements, and close attention to hydration.
Pureed and soft foods, protein first. Desk work resumes from around week two. Supplements begin properly.
Gradual return to normal solid foods in small, well-chewed portions. Exercise resumes progressively.
Most weight comes off over this period: typically 60–80% of excess body weight. Nutritional bloods monitored throughout.
Multivitamin, B12, iron, calcium and vitamin D indefinitely. A longer bypassed segment means deficiency risk is real and monitoring is essential.
60–80g daily, eaten before anything else, to protect muscle mass during rapid weight loss.
Burning behind the breastbone or a bitter taste may indicate bile reflux. It is treatable, and conversion to a Roux-en-Y resolves it if it persists.
Anti-inflammatory painkillers cause ulcers at the join. Use paracetamol, and tell any doctor treating you about your surgery.
Stop fluids thirty minutes before and after eating, so food is not washed through the gastric tube.
Nutritional monitoring every year without exception. Deficiencies develop silently and are far easier to correct early.
Bile reflux is the one complication distinctive to this operation. It affects a minority, is usually manageable with medication, and where it is not, conversion to a Roux-en-Y resolves it definitively.
Book a consultation with a bariatric specialist if any of the following apply.
Bariatric surgery is covered by most insurers in India where BMI criteria are met, and our team handles the pre-authorisation. These are the self-pay ranges.
| Procedure | Estimated Cost |
|---|---|
| Consultation & bariatric assessment Per visit | ₹1,000 – ₹2,000 |
| Complete pre-operative workup Bloods, endoscopy, ultrasound, cardiac and sleep review | ₹20,000 – ₹40,000 |
| Laparoscopic mini gastric bypass Two to three nights’ stay, staplers included | ₹3,20,000 – ₹5,00,000 |
| Robotic-assisted mini bypass Three nights’ stay | ₹4,50,000 – ₹6,50,000 |
| Revision sleeve to mini bypass Three to four nights’ stay | ₹4,00,000 – ₹6,00,000 |
| Follow-up & dietitian programme First year, with nutritional monitoring | ₹15,000 – ₹30,000 |
A single anastomosis uses fewer cartridges and less theatre time, which is why this operation costs somewhat less.
Revising a previous sleeve involves adhesions and a longer operation than a first-time procedure.
Very high BMI, sleep apnoea or heart disease means longer theatre time and closer post-operative monitoring.
A shared ward, a twin-sharing room or a private suite: the largest single swing in most estimates.
We are empanelled with most major insurers, and our team files the pre-authorisation for you.
Every figure above is an indicative range, not a quote. After your consultation you are given a written, fixed-cost estimate, and that is the number you pay, with no additions once treatment begins.
What patients treated here can expect:
One anastomosis instead of two, with less time under anaesthetic.
60–80% of excess body weight, comparable to a Roux-en-Y.
The intestine is never divided, so there are no defects to herniate through.
The bariatric and gastrointestinal surgeon who performs mini gastric bypass at our HITEC CITY hospital.

Senior Consultant: Bariatric & Gastrointestinal Surgery
MBBS, MS, FRCS (UK), DLS (France)
28 years experience
Reviews from patients treated for bariatric and gastrointestinal conditions at Lux Hospitals, Hyderabad.
Written by Dr. Tagore Mohan Grandhi on bariatric surgery and metabolic health.

Dr. Tagore Mohan Grandhi

Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Common questions about mini gastric bypass, its results, and what surgery costs at Lux Hospitals.
Still have questions? Call us at 079 6908 4422
Still have questions? Message us on WhatsApp at 079 6908 4444
Laparoscopic mini gastric bypass with dietitian-led follow-up, and a fixed-cost estimate and insurance check before treatment begins.
Plot No.116, Lumbini Avenue, HITEC CITY, Near IKEA, Hyderabad – 500032













