



Dr. Samhitha Reddy
Consultant Proctologist & Laparoscopic Surgeon
MBBS, MS, FMAS, FISCP, DMAS
- 8 Yrs
- ASCRS Member
Colon cancer is among the most treatable of the common cancers when it is found early. Caught at stage I it is cured in the great majority of patients; caught at stage IV the picture is very different. Almost nothing else in oncology rewards early detection so directly.
Surgery is the mainstay, and modern surgery is done through keyhole incisions. Our gastrointestinal surgeon at Lux Hospitals, HITEC CITY performs laparoscopic colectomy with proper lymph node clearance, working alongside oncology for the chemotherapy that follows where it is needed.
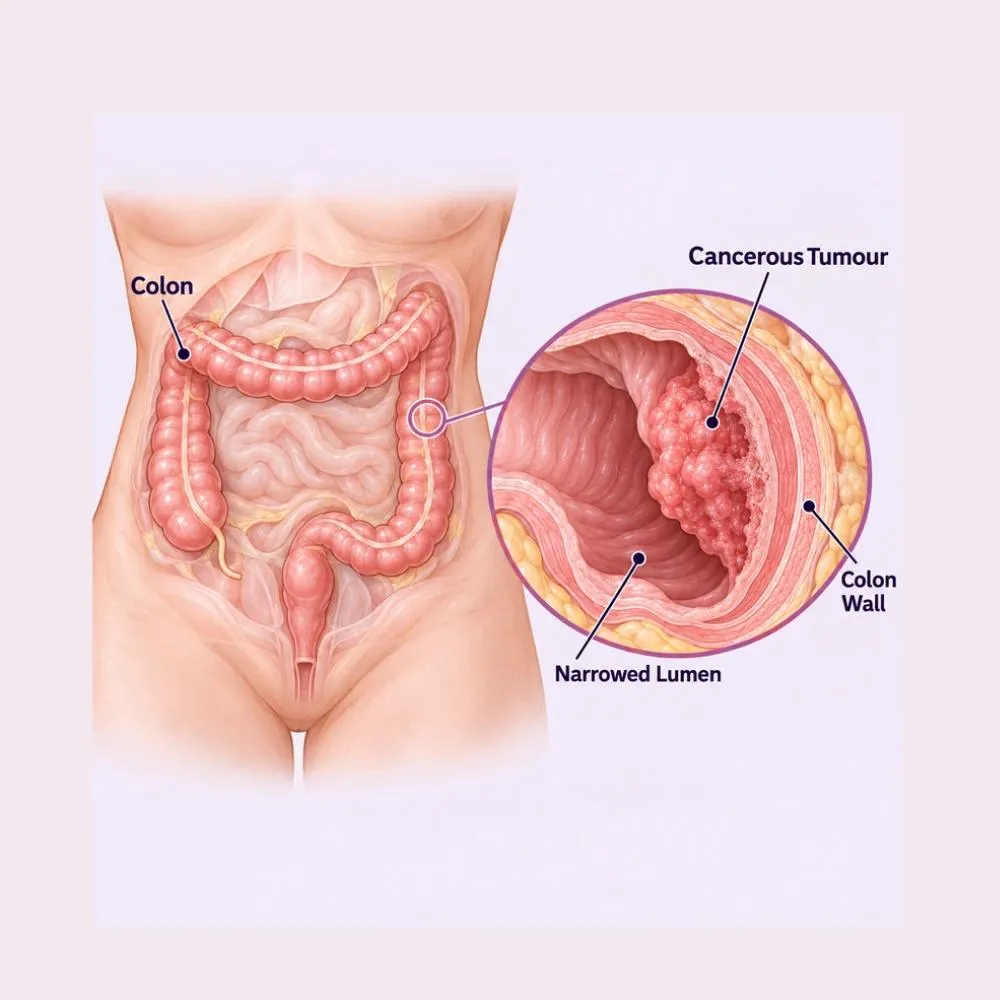
Colon cancer is a malignant growth arising from the inner lining of the large bowel. The overwhelming majority develop from adenomatous polyps over ten to fifteen years, which is why removing polyps prevents the cancer, and why screening works so well in this disease specifically.
Staging determines everything about treatment and outlook. Stage I is confined to the inner layers of the bowel wall. Stage II has grown through the wall but not reached lymph nodes. Stage III has spread to nearby lymph nodes. Stage IV has spread to distant organs, most often the liver or lungs.
The distinction between colon and rectal cancer matters surgically even though they are often grouped as colorectal cancer. Colon cancer is treated primarily with surgery, with chemotherapy afterwards for higher stages. Rectal cancer, sitting in the confined space of the pelvis, usually needs radiotherapy and chemotherapy before surgery.
Most colon cancers are sporadic, arising without an inherited cause, but several factors substantially raise the risk, and a good number are modifiable.
The dominant risk factor. Incidence rises steadily with age, which is why routine screening begins at this point.
The direct precursor. Having had adenomatous polyps significantly raises your risk, and having them removed lowers it.
A first-degree relative with colorectal cancer roughly doubles the risk and means screening should start earlier than forty-five.
Lynch syndrome and familial adenomatous polyposis carry very high lifetime risk and require dedicated surveillance from a young age.
Long-standing ulcerative colitis or Crohn’s colitis raises risk substantially, requiring surveillance from eight years after diagnosis.
High intake of red and processed meat with low fibre is consistently associated with increased risk.
Both independently raise risk, and regular physical activity is one of the more reliably protective factors.
Both increase risk in a dose-related way, and both are modifiable at any age.
Around a quarter of patients have a family history, and a smaller proportion an identifiable inherited syndrome. That is worth establishing, because it changes screening for your relatives as much as treatment for you.
Early colon cancer frequently causes no symptoms at all. When symptoms do appear, they are easily attributed to something more common, which is how the diagnosis gets delayed.
Common symptoms
Systemic and late symptoms
Unexplained iron deficiency anaemia in any adult over forty warrants a colonoscopy, even with no bowel symptoms at all. A right-sided colon cancer often bleeds slowly and silently, and anaemia is its only sign.
Colonoscopy with biopsy makes the diagnosis. Imaging then establishes the stage, and the stage determines the treatment plan entirely.
The definitive test. It visualises the tumour, takes tissue for diagnosis, and examines the rest of the colon for synchronous tumours or polyps.
Staging imaging that assesses local extent and looks for spread to the liver, lungs and lymph nodes.
Full blood count for anaemia, liver and kidney function, and the tumour marker CEA: most useful as a baseline for tracking response afterwards.
Tumour type and grade, plus MSI and RAS/BRAF testing, which guide chemotherapy choice and can identify Lynch syndrome.
Used in selected cases to clarify equivocal findings or to assess suitability for surgery on metastatic disease.
Where a tumour obstructs the colon and the scope cannot pass, to assess the colon beyond the blockage before surgery.
Every case is discussed at a multidisciplinary meeting (surgeon, oncologist, radiologist and pathologist together) before a treatment plan is agreed. That discussion is standard practice, not an optional extra.
Surgery is the primary treatment for colon cancer at every stage where the tumour can be removed. Chemotherapy is added according to stage and pathology.
Removal of the affected segment with its lymph node basin through keyhole incisions. Oncologically equivalent to open surgery, with less pain and faster recovery.
Removal of the right or left half of the colon depending on tumour position, with the healthy ends rejoined.
A larger resection for tumours at flexures, multiple synchronous tumours, or in patients with Lynch syndrome.
The same operation with robotic instrumentation, offering enhanced precision in confined anatomical spaces.
Removing colon cancer that has spread to the liver can still be curative in carefully selected patients, and is worth assessing for.
For obstruction or perforation, sometimes with a stoma initially. A colonic stent may relieve obstruction and allow planned surgery instead.
Given after surgery for stage III and high-risk stage II disease, to eliminate microscopic cells and reduce recurrence.
For stage IV disease, to control the cancer, relieve symptoms and extend life, often for a considerable period.
Anti-EGFR and anti-VEGF agents used in advanced disease, selected on the basis of RAS and BRAF mutation testing.
Highly effective in the subset of tumours with microsatellite instability, which is why MSI testing is done routinely.
Rarely used for colon cancer specifically, in contrast to rectal cancer where it is central. Reserved for selected situations.
Stage I disease usually needs surgery alone. Stage III needs surgery plus chemotherapy. Stage II sits in between, and the decision there depends on pathology features discussed with you individually.
A two to three hour keyhole operation removing the tumour together with its blood supply and lymph nodes, with a five to seven night stay.
Laparoscopic colectomy
Staging complete and the case discussed at the multidisciplinary meeting. Bowel preparation, antibiotics, and anaesthetic and nutritional assessment.
General anaesthetic. The abdomen is inflated with carbon dioxide and four to five ports are placed.
The liver and peritoneal surfaces are inspected for deposits that imaging may not have shown, before the resection is committed to.
The feeding artery is divided at its origin. This is what harvests the full lymph node basin: an oncological principle, not a technical preference.
The colon segment is freed with adequate margins either side of the tumour and removed through a small incision, protected in a bag.
The healthy ends are rejoined with a stapler or by hand, and the join tested for leaks. A stoma is formed only where an immediate join would be unsafe.
Enhanced recovery protocol with early feeding and mobilisation. Home after five to seven nights, with final pathology in about a week.
At least twelve lymph nodes must be examined for the staging to be reliable. If fewer are retrieved, the pathological stage is uncertain, which is why the extent of the resection matters as much as removing the tumour itself.
Colon cancer surgery is judged on margins and lymph node yield, and on the recovery that follows. Here is why patients trust us:
Led by Dr. Tagore Mohan Grandhi, with fellowships in robotic surgery (Korea) and 28 years of gastrointestinal surgical experience.
Full staging with molecular testing, and every case discussed by surgeon, oncologist, radiologist and pathologist together.
From the first consultation through to post-treatment follow-up, with one team throughout.
Our hospital is in HITEC CITY, near IKEA: easily reachable from across Hyderabad.
Recovery from surgery takes six to eight weeks. Where chemotherapy follows, the overall pathway extends across six months or more.
Enhanced recovery protocol: sips of fluid the same evening, out of bed the next day, and diet advanced progressively.
Bowel function returns, usually by day three or four. Home once eating, mobile and comfortable on oral painkillers.
Final pathology discussed and the stage confirmed. The need for chemotherapy is decided at this point. Desk work resumes from around three weeks.
Full physical recovery from surgery. Chemotherapy, where indicated, usually begins six to eight weeks after the operation.
Structured surveillance: clinical review and CEA every three to six months, annual CT, and colonoscopy at one year then at intervals.
Most recurrences occur within the first three years, and many are treatable when found early. Surveillance is what finds them.
Adequate protein and calories support healing and help you tolerate chemotherapy. Dietitian input is part of the pathway.
Walking from day one, building progressively. Regular exercise after treatment is associated with better long-term outcomes.
First-degree relatives need screening earlier than the general population. This is one of the most useful things you can do for them.
Fever, worsening abdominal pain, vomiting, no bowel movement with distension, or wound discharge.
At one year after surgery, then at intervals. A new primary cancer can develop elsewhere in the colon.
Five-year survival is above ninety per cent for stage I disease and falls with each stage. That gradient is the whole argument for screening, and for taking a change in bowel habit seriously rather than waiting.
Book a consultation if any of the following apply.
Cancer treatment is a pathway rather than a single procedure. These are the ranges for its main components.
| Procedure | Estimated Cost |
|---|---|
| Consultation & assessment Per visit | ₹1,000 – ₹2,000 |
| Colonoscopy with biopsy Including histopathology | ₹15,000 – ₹30,000 |
| Complete staging workup CT, bloods, CEA and molecular testing | ₹30,000 – ₹70,000 |
| PET-CT, where indicated Selected cases only | ₹25,000 – ₹45,000 |
| Laparoscopic colectomy Five to seven nights’ stay | ₹3,00,000 – ₹5,50,000 |
| Robotic-assisted colectomy Five to seven nights’ stay | ₹4,50,000 – ₹7,50,000 |
| Adjuvant chemotherapy Per cycle; typically 6–12 cycles | ₹40,000 – ₹1,20,000 |
Stage I usually means surgery alone. Stage III adds months of chemotherapy, and stage IV involves prolonged systemic treatment.
A segmental colectomy, an extended resection, and surgery combined with liver resection differ substantially in complexity and stay.
Targeted agents and immunotherapy are considerably more expensive than standard chemotherapy, and are used where testing indicates them.
A shared ward, a twin-sharing room or a private suite: the largest single swing in most estimates.
We are empanelled with most major insurers, and our team files the pre-authorisation for you.
Every figure above is an indicative range, not a quote. After your consultation you are given a written, fixed-cost estimate, and that is the number you pay, with no additions once treatment begins.
The gastrointestinal and colorectal surgeon who treats colon cancer at our HITEC CITY hospital.

Senior Consultant: Bariatric & Gastrointestinal Surgery
MBBS, MS, FRCS (UK), DLS (France)
28 years experience
Reviews from patients treated for colorectal and gastrointestinal conditions at Lux Hospitals, Hyderabad.
Written by Dr. Tagore Mohan Grandhi on bowel screening, digestive health and colorectal surgery.

Dr. Tagore Mohan Grandhi

Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Dr. Tagore Mohan Grandhi
Common questions about colon cancer, its treatment, and what care costs at Lux Hospitals.
Still have questions? Call us at 079 6908 4422
Still have questions? Message us on WhatsApp at 079 6908 4444
Complete staging, multidisciplinary planning and laparoscopic surgery, with costs and insurance confirmed before treatment begins.
Plot No.116, Lumbini Avenue, HITEC CITY, Near IKEA, Hyderabad – 500032













