



Dr. Samhitha Reddy
Consultant Proctologist & Laparoscopic Surgeon
MBBS, MS, FMAS, FISCP, DMAS
- 8 Yrs
- ASCRS Member
Interstitial cystitis causes bladder pain and a relentless need to pass urine, often thirty or more times a day, with urine tests that come back repeatedly clear.
Most people with it have been treated for urinary infection several times before anyone names the actual condition. Our urologists at Lux Hospitals, HITEC CITY make the diagnosis properly and build a treatment plan in steps, because this condition responds to persistence rather than to a single intervention.
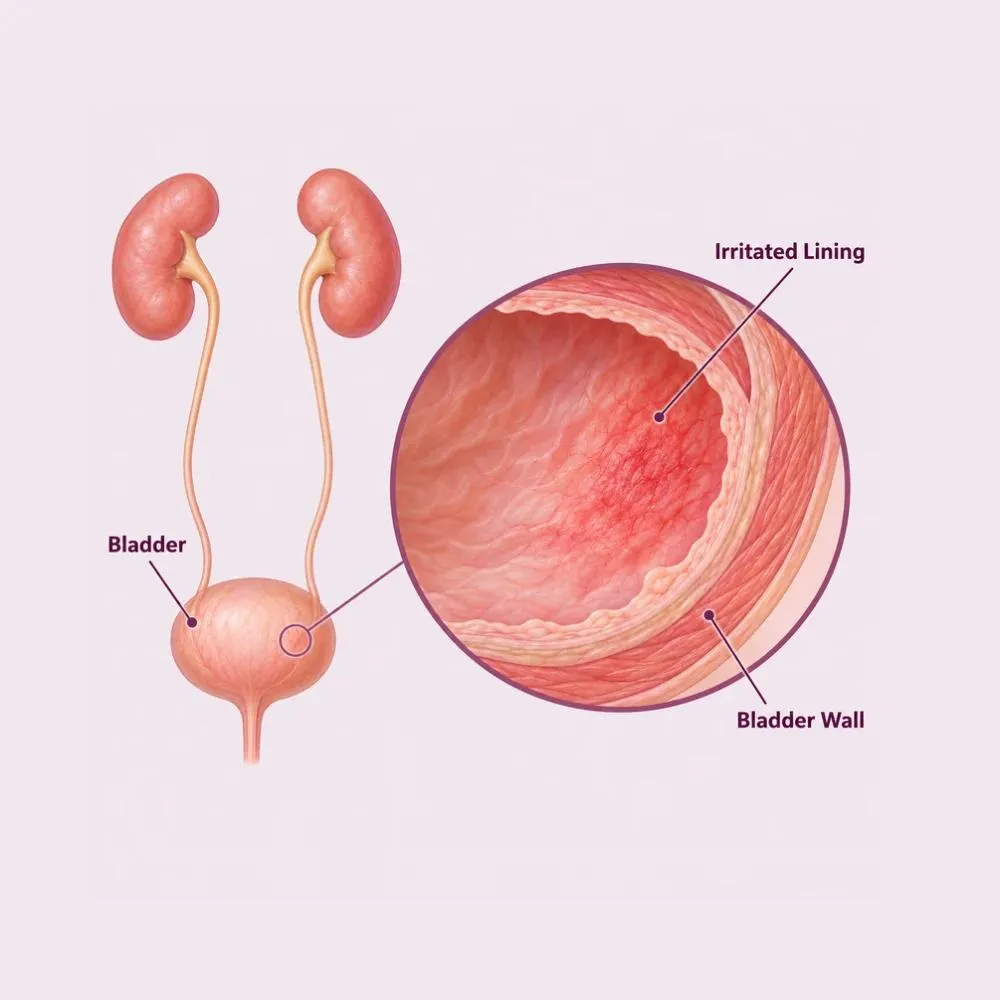
Interstitial cystitis, now more often called bladder pain syndrome, is chronic bladder pain or pressure with urinary urgency and frequency, lasting more than six weeks, without infection or another identifiable cause. It is a diagnosis of exclusion: everything else has to be ruled out first, which is why it takes an average of several years to reach.
The leading explanation is a defect in the glycosaminoglycan layer, the protective coating lining the inside of the bladder. When that layer is deficient, substances in urine (particularly potassium) penetrate into the bladder wall and irritate the nerves and muscle beneath. Over time those nerves become sensitised, so signals that would normally register as mild filling are experienced as pain.
The condition affects women considerably more often than men, typically presenting between thirty and fifty. It runs a fluctuating course, with flares lasting days to weeks separated by better periods. It is not an infection, it is not contagious, it does not become cancer, and it is not psychological, though the sleep deprivation and disruption it causes have very real effects on mood.
The cause is not fully established, and several mechanisms probably act together in different people.
A deficient glycosaminoglycan layer allows irritants in urine, especially potassium, to penetrate the bladder wall. The most widely accepted mechanism.
Bladder nerves become hypersensitive, so normal filling is registered as pain. This explains why symptoms persist even when the bladder looks normal.
Increased numbers of activated mast cells in the bladder wall release histamine and inflammatory mediators, which is why some patients respond to antihistamines.
The association with lupus, Sjögren’s syndrome and other autoimmune conditions suggests an immune component in some cases.
Chronically tight, spasming pelvic floor muscles both cause and are caused by bladder pain, and treating them helps a substantial proportion.
Symptoms sometimes begin after a genuine urinary infection or pelvic surgery, as though the initial insult sets the sensitisation in motion.
The overlap with fibromyalgia, irritable bowel syndrome and chronic fatigue points to a shared tendency toward amplified pain processing.
Nothing you have done causes interstitial cystitis. It is not poor hygiene, not a hidden infection, and not stress, though stress and poor sleep undoubtedly make flares worse once the condition is established.
The combination of pain that eases on voiding and frequency without infection is what distinguishes it.
Core symptoms
Associated features
The pattern that should raise suspicion is repeated courses of antibiotics for a urinary infection that the cultures never actually confirm. That is the commonest route to a delayed diagnosis.
There is no single confirmatory test. The diagnosis is made by excluding everything else in someone with the characteristic pattern.
Repeatedly negative cultures in the presence of symptoms is itself an important finding, and one of the strongest pointers to the diagnosis.
A three-day record of voids, volumes, pain and fluid intake, with validated questionnaires. This quantifies severity and tracks response to treatment.
Urine cytology, imaging and assessment for stones, tumour, endometriosis and gynaecological causes: all of which can mimic it.
The bladder is inspected and gently distended under anaesthesia. Glomerulations or a Hunner lesion support the diagnosis, and distension itself is often therapeutic.
Taken during cystoscopy to exclude carcinoma in situ, which can present identically, and to assess mast cell infiltration.
Examination for pelvic floor muscle tenderness and spasm, which is present in a large proportion and is directly treatable.
Finding a Hunner lesion changes the treatment substantially: that subgroup responds well to direct treatment of the lesion itself, which is why cystoscopy matters rather than treating everyone identically.
Treatment works up in steps. Most people need a combination, and finding the right one takes time and patience.
Identifying and avoiding trigger foods (commonly citrus, tomato, coffee, alcohol, carbonated drinks, artificial sweeteners and spicy food) using an elimination approach.
Gradually extending the interval between voids to increase functional capacity. Slow, but genuinely effective for frequency.
Manual therapy to release tight pelvic floor muscles. One of the best-evidenced treatments, and notably not Kegel exercises, which make it worse.
Thought to help restore the bladder’s protective lining. It requires three to six months before benefit is judged.
A low-dose tricyclic that reduces nerve sensitisation, calms urgency and improves sleep. Used for pain modulation, not depression.
Hydroxyzine and similar drugs, targeting the mast cell component, particularly where there is a history of allergy.
Medication placed directly into the bladder through a fine catheter (DMSO, heparin, lidocaine or hyaluronic acid) typically weekly for six to eight weeks.
Controlled stretching of the bladder under anaesthesia. Both diagnostic and therapeutic, with relief lasting months in many patients.
Fulguration or steroid injection of the lesion, which produces marked and often durable improvement in this specific subgroup.
Injected into the bladder wall to reduce urgency and pain. Effective for several months, and repeatable.
An implanted device stimulating the sacral nerves to normalise the signals between bladder and brain. Trialled temporarily before permanent implantation.
Bladder augmentation or diversion, reserved for severe refractory disease after everything else has genuinely been tried.
Kegel exercises make interstitial cystitis worse rather than better. The pelvic floor in this condition is usually too tight already, and it needs releasing rather than strengthening: a distinction that is frequently got wrong.
Treatment proceeds through steps, moving on only when a step has been given a fair trial.
Stepped, long-term management programme
Excluding infection, stones, tumour and gynaecological causes, with cystoscopy and hydrodistension where the picture warrants it.
Explaining what the condition is and is not, and setting realistic expectations: this is managed rather than cured, and improvement is gradual.
Removing common triggers for two to four weeks, then reintroducing them one at a time to identify your specific ones.
Referral for manual release therapy, typically weekly for eight to twelve sessions, with home techniques between.
Amitriptyline, antihistamine or pentosan polysulfate, each given an adequate trial of three months before being judged.
A course of weekly instillations, usually six to eight, with maintenance instillations afterwards where they have helped.
Hydrodistension, botulinum toxin or sacral neuromodulation for symptoms not controlled by the earlier steps.
The commonest reason treatment appears to fail is that each step was abandoned too soon. Pentosan polysulfate needs three to six months, and amitriptyline several weeks at a stable dose, before either can fairly be judged.
This condition is chronically under-diagnosed and frequently mistreated as recurrent infection. Here is why patients trust us:
Proper exclusion of other causes, cystoscopy where indicated, and a named diagnosis instead of another course of antibiotics.
Diet and physiotherapy through to instillations, hydrodistension, botulinum toxin and neuromodulation, escalating only as needed.
From the first consultation through to post-treatment follow-up, with one team throughout.
Our hospital is in HITEC CITY, near IKEA: easily reachable from across Hyderabad.
This is a condition managed over years. Improvement is real but gradual, and flares continue to happen.
Diagnosis established and dietary elimination begun. Some people notice meaningful improvement from diet alone within this period.
Pelvic floor physiotherapy underway and oral medication started. Amitriptyline in particular improves sleep early, which itself helps considerably.
Oral treatment can now be fairly judged. Instillations added where symptoms remain troublesome.
Most people have found a workable combination by this point. Advanced options are considered where they have not.
Ongoing management with flare plans, periodic review and maintenance treatment. Symptoms fluctuate rather than following a steady course.
Triggers are individual and cannot be predicted. A diary is the only reliable way to identify yours, and it also tracks whether treatment is working.
The pelvic floor in this condition is usually too tight. Strengthening it makes symptoms worse: it needs releasing instead, which is what physiotherapy does.
Pentosan polysulfate needs three to six months and amitriptyline several weeks at a stable dose. Abandoning them early is the commonest reason treatment seems to fail.
Increased fluids to dilute urine, heat, strict avoidance of triggers, and a short course of a urinary alkaliniser. Knowing what to do reduces how disabling flares feel.
Night-time frequency is deeply disruptive and sleep deprivation amplifies pain. Treating the nocturia is often the change patients value most.
Chronic pelvic pain is isolating and frequently dismissed. Psychological support and patient groups genuinely help, and needing them is not a sign the pain is imagined.
Interstitial cystitis is not cured, but it is very often controlled. Most people, with the right combination, reach a point where the condition sits in the background rather than dictating the day.
Book a consultation if any of the following apply.
This is a long-term condition, so the meaningful figure is the ongoing cost rather than any single procedure.
| Procedure | Estimated Cost |
|---|---|
| Consultation Per visit; regular review needed | ₹800 – ₹1,500 |
| Diagnostic workup Urine tests, cytology, ultrasound | ₹4,000 – ₹10,000 |
| Cystoscopy with hydrodistension Day care, general anaesthesia | ₹45,000 – ₹85,000 |
| Monthly oral medication Varies with the combination used | ₹1,000 – ₹5,000 |
| Bladder instillation Per session; course of six to eight | ₹4,000 – ₹9,000 |
| Pelvic floor physiotherapy Per session; eight to twelve sessions | ₹800 – ₹2,000 |
| Botulinum toxin injection Includes the drug; lasts several months | ₹55,000 – ₹1,10,000 |
| Sacral neuromodulation Dominated by the device cost | ₹5,50,000 – ₹9,00,000 |
Many people are managed on diet, physiotherapy and oral medication at a few thousand rupees monthly. Only refractory cases reach the expensive interventions.
This subgroup responds well to direct treatment of the lesion, which is far less costly than neuromodulation.
An induction course is six to eight sessions. Maintenance instillations, where helpful, continue at longer intervals.
A shared ward, a twin-sharing room or a private suite: the largest single swing in most estimates.
We are empanelled with most major insurers, and our team files the pre-authorisation for you.
Every figure above is an indicative range, not a quote. After your consultation you are given a written, fixed-cost estimate, and that is the number you pay, with no additions once treatment begins.
The urologists who treat interstitial cystitis at our HITEC CITY hospital.

Consultant Urologist & Andrologist
MBBS, MS, DrNB (Urology)
10 years experience

Consultant Urologist & Andrologist
MBBS, MS, MCh (Urology)
9 years experience
Reviews from patients treated for bladder and urological conditions at Lux Hospitals, Hyderabad.
Written by Dr. Vipin Reddy B on bladder health and urological care.

Dr. Vipin Reddy B
Dr. Vipin Reddy B
Dr. Vipin Reddy B
Dr. Vipin Reddy B

Dr. Vipin Reddy B

Dr. Vipin Reddy B
Common questions about interstitial cystitis, bladder pain syndrome and what treatment costs at Lux Hospitals.
Still have questions? Call us at 079 6908 4422
Still have questions? Message us on WhatsApp at 079 6908 4444
A proper diagnosis and a stepped treatment plan for interstitial cystitis, with costs shared upfront.
Plot No.116, Lumbini Avenue, HITEC CITY, Near IKEA, Hyderabad – 500032













